Understanding the Anion Gap?
The anion gap is a calculated value used to assess electrolyte balance and overall acid-base status in adults. It compares the major measured ions in blood chemistry, especially sodium and chloride, and assists clinicians in estimating the amount of unmeasured anions in the bloodstream.
Although the number is simple, its meaning is wide-ranging. A shift in the anion gap can point to a shift in serum electrolytes, an increase in systemic acid load, or a problem that affects how the body maintains acid-base balance. Because it reflects the connection between several lab values, the anion gap is a helpful diagnostic tool rather than a standalone diagnosis.
In adult care, the anion gap is often reviewed alongside the electrolyte panel, bicarbonate concentration, and other blood chemistry results. It can help identify metabolic acidosis, especially when the cause is not immediately obvious. When interpreted correctly, it offers a fast clue to whether acid has accumulated in the body or whether certain proteins and ions are affecting the measurement.
How to Work With an Anion Gap Calculator
An anion gap calculator is designed to carry out the calculation rapid and accurate. You input the numbers for serum sodium, serum chloride, and serum bicarbonate, and the calculator returns the anion gap. This is particularly useful when checking multiple lab values or when you want a quick check during medical interpretation.
To use the calculator properly, ensure you are entering the same type of values the formula expects. Most calculators use concentrations from a standard blood chemistry panel. If your lab report lists a bicarbonate or total CO2 value, check that it is the intended value for the calculation. Even a small input mismatch can change the result enough to affect interpretation.
- Provide the serum sodium value exactly as reported. Provide the serum chloride value from the same blood draw. Provide the serum bicarbonate value from the same panel. Review the output in the context of the patient’s symptoms and other lab findings.
An anion gap calculator is best viewed as a clinical interpretation aid. It does not replace assessment of the patient’s history, medication use, renal function, or possible toxic ingestion. It provides a number, but the number only becomes useful when matched to the broader picture.
Anion Gap Formula and Calculation Steps
The classic anion gap formula is:
Na minus Cl minus HCO3
In clinical terms, that means subtracting serum chloride and serum bicarbonate from serum sodium. Certain labs and calculators display the equation as Na minus Cl with bicarbonate added in the final step, but the principle is the same: the result estimates the gap between measured cations and measured anions.
Here is the simple calculation workflow:
- Start with the serum sodium value. Take away the serum chloride value. Subtract the serum bicarbonate value. The result is the anion gap.
For example, if sodium is 140, chloride is 102, and bicarbonate is 24, the anion gap is 14. That number may land within a typical adult range depending on the lab’s reference interval.
One reason the calculation matters is that it reflects the presence of unmeasured anions such as proteins, phosphate, sulfate, organic acids, and other components not directly listed in the routine electrolyte panel. Since albumin is a major unmeasured anion, changes in albumin can significantly affect the result. That is why some clinicians also consider an albumin-adjusted or corrected value.
Typical Anion Gap Range in Adults
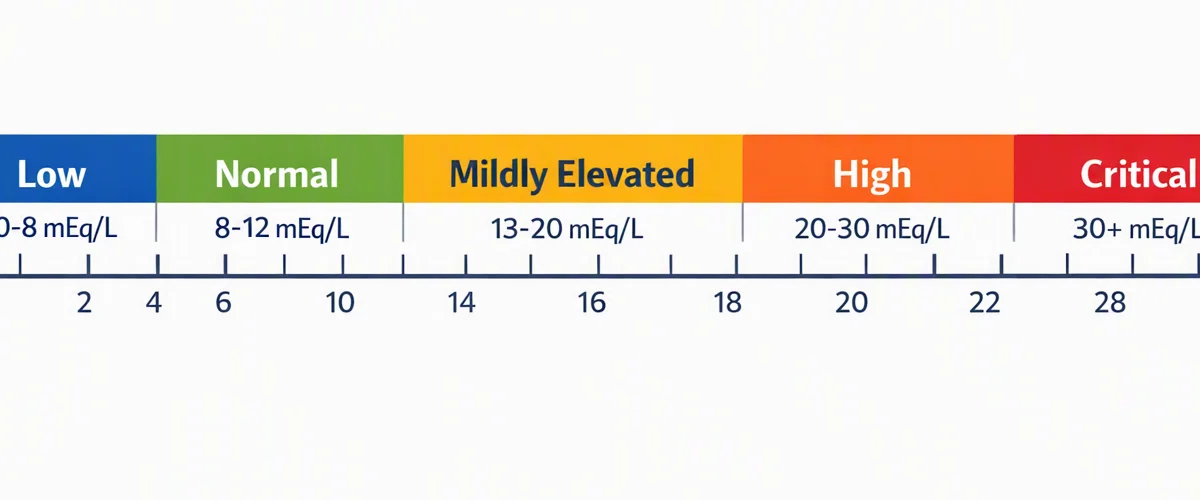
The normal anion gap range in adults depends on the laboratory method and the analyzer used. There is not one universal value, because laboratory values can vary based on calibration, measurement approach, and local reporting practices. For that reason, the best reference interval is the one provided by the lab that performed the adult blood test.
In many settings, the normal anion gap is considered relatively narrow, but it may differ enough between labs that a borderline result should be interpreted carefully. A value that is normal in one system may be mildly abnormal in another. This is why the reported normal interval should always be checked before drawing conclusions.
When reviewing a result, focus on whether the value is significantly different from the expected range rather than whether it is only just above or under the cutoff. Small differences may reflect ordinary biological variation, lab variation, or a mild shift in electrolyte balance.
Because the anion gap is influenced by albumin, a person with low albumin may appear to have a “usual” or even low value despite a clinically important problem. That is one reason the number should never be interpreted by itself.
Increased Anion Gap: Typical Causes
A high anion gap often suggests high anion gap metabolic acidosis, a type of metabolic acidosis in which acidic substances collect and boost the amount of unmeasured anions. This pattern is important because it can point toward a serious underlying disorder that needs prompt attention.
Frequent causes are lactic acidosis, ketoacidosis, and renal failure. Each can create a systemic acid load that increases the anion gap.
- Lactic acidosis: Often associated with tissue hypoperfusion, sepsis, hypoxia, or other conditions that increase lactate elevation. Ketoacidosis: Appears in uncontrolled diabetes, starvation, alcohol use, or other states of ketone accumulation. Renal failure: Poor elimination of acids and reduced renal function can allow acids to build up.
Other causes of a high result may include certain toxic ingestion scenarios, which can also alter the osmolar gap. That is why a high anion gap should prompt a broader search for the source of acid accumulation rather than stopping the evaluation.
Clinically, a high value is usually interpreted alongside symptoms, vital signs, medication history, and an arterial blood gas. The aim is not only to label the abnormality but to find the process behind it.
Decreased Anion Gap: Likely Reasons
A low anion gap is not as common than a high one, but it can still be clinically meaningful. The most common explanations include hypoalbuminemia, multiple myeloma, lithium toxicity, and laboratory error.
Hypoalbuminemia is the most frequent reason because albumin is a major unmeasured anion. When albumin falls, the calculated gap may also fall even if acid-base status has not shifted much. This makes the finding easy to overlook unless the clinician considers protein levels and overall clinical context.
Multiple myeloma can lower the anion gap because abnormal positively charged proteins may alter the balance of measured and unmeasured ions. In some cases, the anion gap becomes a clue that prompts additional evaluation for a plasma cell disorder.
Lithium toxicity may also produce a low value because lithium acts as an unmeasured cation. If a patient is taking lithium and the result is unexpectedly low, medication review becomes important.
Finally, laboratory error or lab variation should always be considered. A single unexpected low result may reflect sample handling issues, instrument problems, or measurement error. Repeating the test is often the best first step when the result does not fit the rest of the picture.
Revised Anion Gap and Albumin Correction
Since albumin strongly influences the anion gap, most clinicians use albumin correction to determine a corrected anion gap. This adjustment helps adjust for low serum albumin and provides a more reliable view of acid-base balance.
The need for correction is simple: when albumin is low, the measured gap may downplay the degree of acid disturbance. An albumin-adjusted result can show a hidden high anion gap that would otherwise be overlooked.
Even though different formulas exist, the general principle is that lower albumin raises the likelihood of diminishing the true gap. In everyday interpretation, if serum albumin is reduced, the raw number should be viewed cautiously and corrected when needed.
This is especially important in patients with chronic illness, malnutrition, liver disease, inflammation, or other conditions associated with low albumin. In those settings, the corrected value often more closely represents the patient’s real biochemical state and allows more reliable clinical interpretation.

Interpreting Results in the Clinical Setting
The anion gap is most helpful when paired with the remainder of the clinical evaluation. An standalone number can be misleading, but a number along with symptoms, exam findings, and additional labs can improve the diagnosis quickly.
When the result is abnormal, review the arterial blood gas, bicarbonate level, and chloride level together. These values help determine whether the patient truly has metabolic acidosis, whether respiratory compensation is present, and whether chloride changes are contributing to the pattern.
A low bicarbonate level with an elevated anion gap strongly suggests metabolic acidosis. A low bicarbonate with a normal gap may suggest a different type of acid-base disorder. A high or low chloride level can also point toward dilutional effects, vomiting, diarrhea, renal tubular problems, or other disturbances in serum electrolytes.
Clinical interpretation should also account for medication use, fluid status, blood pressure, kidney function, and possible exposure to toxins. In other words, the anion gap is a https://anion-gap-results691.urbanvellum.com/posts/how-lactic-acidosis-impacts-the-anion-gap signal, not the definitive result.
Potential Limitations of the Anion Gap Calculator
Even a well-designed anion gap calculator has limitations. It depends on correct input, accurate lab reporting, and the assumption that the measured values are reliable. If any of these elements are off, the result may be misleading.
Measurement error can occur with any blood test. Small errors in sodium, chloride, or bicarbonate can shift the number enough to change interpretation, especially when the value is borderline.
Lab variation is another issue. Different analyzers and methods may produce slightly different results, which affects the reported normal anion gap range. This is why comparison with the local reference interval matters more than comparing numbers from different systems.
The calculator also does no longer diagnose every source of acid-base imbalance. Some individuals may have overlapping acid-base disorders, which can hide the expected trend. In addition, the osmolar gap may be significant when toxic alcohol exposure or another toxic ingestion is suspected. The anion gap and osmolar gap can support each other, but they are not interchangeable.
In the end, the calculator supports decision-making, but it does not replace clinical reasoning, repeat testing when needed, or broader diagnostic evaluation.

Frequently Asked Questions
What is an anion gap calculator used for in adults?
An anion gap calculator is used to efficiently calculate the anion gap from common blood chemistry values. In adults, it helps evaluate metabolic acidosis, detect possible acid accumulation, and support the broader evaluation of electrolyte balance and acid-base status.
What is a normal anion gap range in adults?
The normal anion gap range in adults depends on the laboratory and analyzer used. Because laboratory values differ, the most accurate answer is the lab’s own reference interval. A result should always be read in relation to that lab’s reported normal range.
What causes a high anion gap?
A high anion gap is commonly caused by high anion gap metabolic acidosis. Frequent causes include lactic acidosis, ketoacidosis, and renal failure. Toxic ingestion and other conditions that increase unmeasured anions can also elevate the value.
Why can albumin change the anion gap result?
Albumin is a major unmeasured anion, so changes in albumin affect the calculated result. When serum albumin is low, the anion gap may appear lower than expected. That is why albumin correction and the corrected anion gap are crucial in many adult patients.
Can one reduced anion gap be a sign of an important condition?
Indeed. A decreased anion gap can occasionally signal an significant problem such as hypoalbuminemia, multiple myeloma, or lithium toxicity. It may also be caused by laboratory error, so a repeat test and doctor evaluation are often needed to determine the underlying cause.