What Is an Anion Gap Calculator?
An anion gap calculator is a simple clinical tool used to calculate the gap between measured electrolytes in the blood, usually based on sodium, chloride, and bicarbonate. This derived number helps determine whether there is an anion gap rise suggestive of metabolic acidosis and related patterns of acid-base imbalance.
In standard serum chemistry interpretation, the calculator assists clinical interpretation by helping identify whether there is an accumulation of unmeasured acid in the bloodstream. Because the body normally maintains tight acid-base balance, even small shifts in laboratory values can indicate an important metabolic derangement.
The main benefit of an anion gap calculator is its diagnostic utility. It does not diagnose a condition by anion gap in chronic kidney disease itself, but it provides a quick way to screen for high anion gap metabolic acidosis, triggering further review of the patient’s symptoms, medications, and possible causes of acid accumulation.
In practice, the calculator is often used alongside the broader anion gap formula, other laboratory values, and the overall clinical picture. That includes looking for signs of electrolyte imbalance, dehydration, and acid-base disturbance that may require timely evaluation.
How the Anion Gap Connects to Alcoholic Ketoacidosis
Alcoholic ketoacidosis is a form of acute metabolic crisis that can occur after heavy alcohol use, little food intake, and ongoing vomiting. The condition is marked by greater ketone production, especially when the body switches off glucose use and into fat metabolism. This results in the buildup of acidic ketones, including beta-hydroxybutyrate, which can raise the anion gap.
In alcoholic ketoacidosis, the blood often shows ketonemia with high levels of ketones, but the pattern may be subtle if only urine ketones are checked. Beta-hydroxybutyrate is especially crucial because it is frequently the dominant ketone in this condition. As these acids gather, they consume bicarbonate, reducing bicarbonate and contributing to metabolic acidosis.
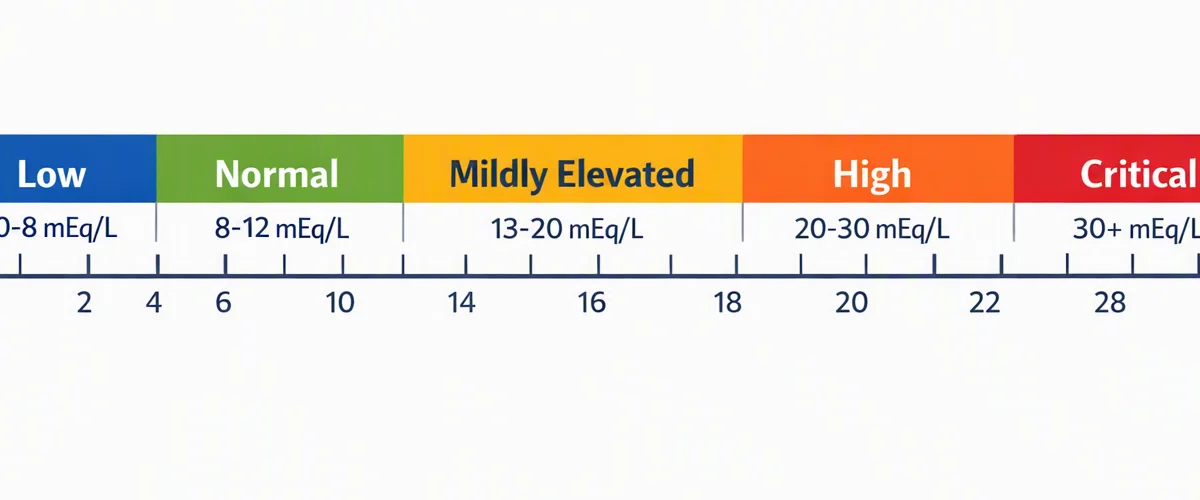
This is why the anion gap calculator is so helpful in this setting. A high value can support suspicion for high anion gap metabolic acidosis, especially when combined with the patient’s history, volume status, and other laboratory findings. It can also be used to separate alcoholic ketoacidosis from other causes of acidosis that may seem similar at first glance.
Alcoholic ketoacidosis often appears in the setting of volume depletion, poor oral intake, and ongoing vomiting. Those factors can worsen acid-base changes and make interpretation more complex. In some cases, the patient may have a mixed acid-base disorder, meaning more than one process is affecting the final pH.
How to Determine the Anion Gap
The standard approach to calculating the anion gap uses sodium, chloride, and bicarbonate. The typical calculation is:
Anion gap = sodium - (chloride + bicarbonate)
These results are usually taken from a basic metabolic panel or other serum chemistry panel. A higher than expected result suggests that unmeasured anions may be present in the blood, which is why the calculator is useful for assessing acid-base disorders.
Albumin also matters because it is a major unmeasured anion. When albumin is low, the measured anion gap can appear artificially normal or only mildly elevated. For that reason, lab result interpretation should consider whether an albumin-corrected anion gap is needed.
To use the calculator accurately, it helps to review each component closely:
- Sodium represents the main measured cation in the formula. Chloride and bicarbonate are the primary measured anions included in the calculation. Albumin influences the expected baseline and may change the interpretation.
Because small changes in these laboratory values can shift the result, clinical interpretation should never rely on the number alone. A patient with alcoholic ketoacidosis may have a clearly abnormal anion gap even before severe pH changes are obvious.
Anion Gap Formula and Albumin Correction
The anion gap formula is straightforward, but assessment becomes less straightforward when albumin is low. Since hypoalbuminemia reduces the baseline anion gap, the uncorrected result may downplay the true degree of acid-base disturbance.
That is why an albumin-corrected anion gap is often useful. Accounting for albumin enhances the corrected anion gap estimate and can uncover a clinically important gap that would otherwise be missed. This matters in patients with poor nutrition, chronic illness, or heavy alcohol use, where low albumin may be common.
A typical reference range for the anion gap changes depending on the laboratory method and whether potassium is included in the formula. The specific cutoffs can change by institution, so interpretation should always use the local reference range rather than assuming one universal normal value.
In alcoholic ketoacidosis, albumin correction can be especially useful because the patient may have multiple contributors to acid-base imbalance. A low albumin level may mask the severity of the high anion gap metabolic acidosis, making the corrected result more informative for clinical interpretation.
Key point: A normal-looking anion gap does not always rule out a significant acid-base disorder if albumin is low or if a mixed process is present.
Usual Lab Findings in Alcoholic Ketoacidosis
Alcoholic ketoacidosis frequently shows a recognizable pattern of laboratory findings, though not each patient shows the same presentation. The core abnormality is typically elevated beta-hydroxybutyrate, which reflects active ketone production and helps support the diagnosis of ketonemia.
Glucose may be reduced, normal, or only somewhat elevated. This can distinguish alcoholic ketoacidosis from diabetic ketoacidosis, where glucose is commonly much higher. However, blending can occur, so glucose alone should not be used as the only discriminator.
Lactate may also be raised, especially if there is poor perfusion, volume depletion, or impaired metabolism. That means some patients have both ketoacidosis and lactic acidosis, which can deepen the high anion gap. Lactate elevation does not exclude alcoholic ketoacidosis; it may simply contribute another layer of acid accumulation.
These findings may include:
- Raised beta-hydroxybutyrate Evidence of ketonemia Low bicarbonate Increased anion gap Fluctuating glucose level Likely lactate elevation
The combination of these laboratory values supports the diagnosis, but the clinical context remains crucial. Symptoms such as vomiting, poor intake, and recent alcohol cessation are especially important in identifying the underlying metabolic derangement.
How to Read Output Correctly
Safe interpretation of the anion gap requires looking beyond the calculator result and reviewing the complete acid-base picture. A patient may have a high anion gap and still have a near-normal pH if another process is also present. That is the hallmark of a mixed acid-base disorder.
For example, vomiting can produce metabolic alkalosis from loss of gastric acid while alcoholic ketoacidosis produces metabolic acidosis. The net pH may appear less abnormal than expected. Because of that, a normal or only slightly abnormal pH should not override other evidence of a serious acid-base disturbance.
An arterial blood gas can help determine whether there is true acidemia, compensation, or an additional respiratory component. Blood gas data, together with serum chemistry, improves lab result interpretation and helps identify the full pattern of metabolic acidosis.
The osmolar gap is another useful piece of information when the diagnosis is uncertain. An elevated osmolar gap may raise concern for toxic alcohol ingestion, especially if the history is unclear. In that setting, the anion gap calculator helps with differential diagnosis, but it should be used as part of toxin screening and broader evaluation rather than as a standalone answer.
Clinical interpretation is safest when all of the following are considered together:
- Patient symptoms and history Serum chemistry results Arterial blood gas Albumin level Osmolar gap Possible mixed acid-base disorder
Main Causes of a High Anion Gap
Alcohol-related ketoacidosis is one cause of high anion gap metabolic acidosis, but it is only one possibility. An elevated gap reflects the buildup of acid from several possible sources, and the differential diagnosis should remain wide.
Key causes include methanol poisoning, lactic acidosis, uremia, and diabetic ketoacidosis. All of these can produce a comparable test pattern, though the history and accompanying findings often vary.
In toxic cases, toxic alcohol ingestion may also create a high anion gap and an increased osmolar gap, especially early on. Such overlap is why careful clinical interpretation matters. If toxic ingestion is suspected, urgent evaluation and toxin screening may be needed.
Other contributors may include renal failure, severe infection, shock, and other forms of metabolic acidosis. The anion gap calculator helps flag the abnormality, but the next step is finding the underlying cause.
For practical differential diagnosis, clinicians often compare patterns such as:
- Acid buildup driven by ketones in alcoholic ketoacidosis Severe hyperglycemia in diabetic ketoacidosis High lactate in lactic acidosis Kidney retention of acids in uremia Possible changes in the osmolar gap with methanol or other toxic alcohol ingestion
When to Seek Urgent Medical Assessment
Alcohol-related ketoacidosis can turn dangerous fast, especially when it is accompanied by ongoing vomiting, dehydration, or impaired mental status. Symptoms may begin with nausea and abdominal discomfort, then lead to weakness, tachycardia, and confusion.
Vomiting and fluid loss are especially concerning because they worsen volume depletion and can intensify the anion gap diabetic ketoacidosis acid-base disturbance. A rapid heartbeat, or tachycardia, may indicate significant physiologic stress or dehydration.
Changes in mental status is a major warning sign and should prompt urgent evaluation. This can reflect severe metabolic derangement, poor perfusion, hypoglycemia, toxic ingestion, or another medical emergency. If symptoms are severe or worsening, immediate medical care is needed.
Anyone with suspected alcoholic ketoacidosis should not rely on a calculator result alone. A high anion gap, low bicarbonate, ketonemia, or abnormal arterial blood gas can point to a condition that needs urgent treatment, including fluids, glucose, electrolyte correction, and close monitoring.
Urgent evaluation is needed if there is:
- Persistent vomiting Severe dehydration Fast heart rate or weakness Mental status changes Suspicion of toxic alcohol ingestion Increasing acid-base imbalance
Common Questions About Anion Gap Calculator and Alcoholic Ketoacidosis
Why would someone use an anion gap calculator for alcoholic ketoacidosis?
An anion gap calculator is used to estimate the anion gap from routine lab values and help identify high anion gap metabolic acidosis. In alcoholic ketoacidosis, it can support the diagnosis when ketones, low bicarbonate, and other laboratory values suggest acid accumulation. It is most useful for clinical interpretation, not as a standalone diagnosis.
How do you calculate the anion gap from sodium, chloride, and bicarbonate?
The standard anion gap formula is sodium - (chloride + bicarbonate). This uses measured serum chemistry values to estimate the amount of unmeasured anions in the blood. If the result is above the local reference range, it suggests an acid-base disturbance such as metabolic acidosis.
Why does alcoholic ketoacidosis to produce a high anion gap?
Alcoholic ketoacidosis produces a high anion gap because the body generates excess acidic ketones, especially beta-hydroxybutyrate. These acids worsen ketonemia, decrease bicarbonate, and contribute to high anion gap metabolic acidosis. Vomiting, poor intake, and volume depletion can make the metabolic derangement more pronounced.
Is albumin useful to correct the anion gap?
Yes, albumin should be taken into account because hypoalbuminemia can make the anion gap appear normal. An albumin-corrected anion gap can better reflect the true acid-base status. This is especially important when interpreting labs in patients with poor nutrition, ongoing disease, or suspected alcoholic ketoacidosis.
What else can cause a high anion gap besides alcoholic ketoacidosis?
Other common causes include diabetic ketoacidosis, lactic acidosis, uremia, and toxic alcohol ingestion such as methanol. These conditions can overlap in symptoms and laboratory findings, so the anion gap calculator should be used as part of a wider differential diagnosis and clinical evaluation.