What the Anion Gap Reflects in Blood Chemistry
The anion gap is a derived value used in medical chemistry to support the interpretation of electrolytes and understand acid-base balance. It reflects the difference between major measured cations and anions in the blood, mainly sodium and chloride, with bicarbonate included in the comparison. Because routine testing does not directly measure every ion in circulation, the anion gap may indicate the presence of unmeasured anions and other shifts in the body’s buffering system.
In practical lab interpretation, the anion gap is a supportive measure rather than a definitive diagnosis. It is often used to assess a possible acid-base disorder, especially when a clinician is trying to determine whether a metabolic disturbance is present. A normal result suggests the measured ions are balanced in a way that fits the expected electroneutrality of plasma, while an abnormal result can point to an electrolyte imbalance or hidden acids that are not obvious from the basic panel alone.
How an Anion Gap Calculator Works
An Anion Gap Calculator applies a straightforward formula to the values provided from a lab report. Most calculators use serum sodium, serum chloride, and serum bicarbonate, and some also include potassium. The calculator then produces a derived value that supports lab interpretation by showing whether the measured ions suggest an acid-base issue.
In the usual approach, the calculator subtracts chloride and bicarbonate from sodium. If potassium is included, the formula may vary slightly, but the basic idea is the same: weigh major measured ions against the expected balance. Because the result is a calculated value, its meaning depends on the surrounding serum electrolytes, the patient’s clinical state, and the interpretive context of the rest of the report.
This makes the calculator valuable as a diagnostic marker in clinical chemistry. It does not replace direct testing or clinical judgment, but it helps identify whether the lab result may reflect an anion deficit, anion excess, or a broader metabolic disturbance.
Conventional Anion Gap Formula and Expected Range
The classic anion gap formula is commonly written as:
Anion gap = sodium − (chloride + bicarbonate)
Certain laboratories also use a potassium-inclusive formula, but the sodium-based version is the most widely recognized in general lab science. The result is then compared with a normal range or reference interval provided by the laboratory performing the test.
The exact reference interval can change because different instruments, reagents, and reporting methods may produce slightly different values. That is why the result should always be interpreted against the lab’s own serum chemistry panel reference interval rather than relying on a universal cutoff. A result that appears abnormal in one lab may fall within another lab’s normal range.
From a lab science perspective, the anion gap is a helpful summary of the relationship between measured ions and unmeasured ions. It is not a direct measurement of acid or base, but rather a calculated clue that may indicate the need for additional testing, including a blood gas or additional chemistry studies.
Revised Anion Gap for Albumin
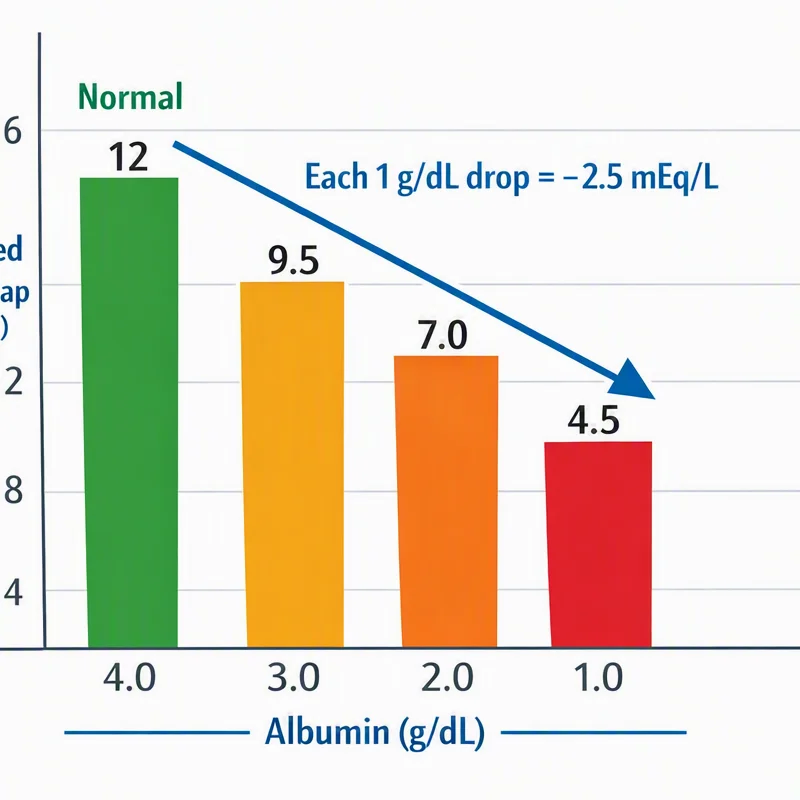
Albumin is a key unmeasured anion in blood, so low albumin can decrease the apparent anion gap. This is why many clinicians and laboratorians use a corrected anion gap when the patient has hypoalbuminemia. Without albumin correction, the result may underestimate the presence of an acid load.
The corrected value is especially useful in patients with illness, inflammation, malnutrition, liver disease, or fluid shifts that reduce albumin concentration. In these cases, the unadjusted anion gap may look normal even though a true acid-base problem exists. An albumin-adjusted interpretation helps reveal the hidden contribution of the reduced protein buffer.
For lab interpretation, albumin correction improves the value of the anion gap as a diagnostic aid. It improves the connection between the numeric result and the patient’s real metabolic state. In other words, the corrected anion gap provides better interpretive context when low albumin could otherwise mask clinically important changes.
Elevated Anion Gap compared with Decreased Anion Gap
A high anion gap usually indicates excess acid or build-up of unmeasured anions. This pattern is often associated with metabolic acidosis, where bicarbonate is depleted as the body buffers acid. A high value is a sign that the balance between measured ions and unseen ions has shifted in a meaningful way.
A decreased anion gap is less common and can be caused by lab or physiologic factors. It may indicate low albumin, abnormal proteins, or analytical issues, among other possibilities. Because the low result can be subtle, it is important to confirm the numbers and review the broader electrolyte panel before reaching conclusions.
Both patterns require careful lab interpretation. A high result often indicates added acids, while a low result may point to reduced negative charge from albumin or analysis-related issues. Either way, the value should be read as part of the complete clinical picture rather than as an isolated finding.
Common Causes of an Elevated Anion Gap
Various factors can shift the anion gap away from the expected range. One of the most important is lactic acidosis, in which lactate accumulates as tissues create energy under stress or inadequate oxygen availability. Another common cause is ketoacidosis, where ketone production goes up and introduces additional acids to the blood.
Renal failure can also lead to an abnormal result because the kidneys are less able to eliminate acid and support normal electrolyte handling. As retained acids and related compounds increase, the gap may rise. In addition, toxins can cause a high anion gap by bringing in unusual acids or by interfering with metabolism in ways that increase acid load.
These causes all fit the same basic pattern: the body accumulates unmeasured ions or loses buffering capacity, and the calculated value rises. In the lab, this makes the anion gap a helpful clue in distinguishing one metabolic disturbance from another.
How to Work with the Calculator Step-by-Step
Working with Anion Gap Calculator is easy when the lab values are available. Begin by locating the input values from the report, then enter the serum sodium, serum chloride, and serum bicarbonate. If supported, include potassium as https://anion-gap-estimator828.wpsuo.com/anion-gap-calculator-for-evaluating-lactate-elevation well.
Once you enter the numbers, review the calculated result and compare it with the lab’s reference range. When the tool provides a corrected output, enter the albumin value so the tool can estimate the corrected anion gap. This is particularly important when hypoalbuminemia is present.
Once the calculation is complete, interpret the result in context. A single number does not diagnose an acid-base disorder by itself. Instead, use it as part of a wider assessment that includes the electrolyte panel, the serum chemistry panel, and any other available clinical information.
Clinical and Laboratory Reading Tips
Good clinical interpretation begins with reviewing whether the result fits the overall picture of acid-base status. If the anion gap is elevated, look for signs of metabolic acidosis and consider whether the patient may have lactic acidosis, ketoacidosis, renal failure, or toxin exposure. If the value is reduced, review albumin, total protein, and the possibility of analytical variation.
A blood gas can be particularly helpful because it provides direct information about pH, carbon dioxide, and bicarbonate handling. When paired with the anion gap, it offers a clearer view of whether there is a true acid-base disorder and whether compensation is occurring. This combination is often more informative than any one lab result alone.
It is also important to think about analytical pitfalls. Small shifts in measured ions can change the calculated value, and differences between instruments can affect the reported reference interval. For this reason, the anion gap should be interpreted alongside the electrolyte panel, the serum chemistry panel, and the patient’s clinical status. That approach improves diagnostic clarity and minimizes the risk of overcalling or missing an abnormality.
Anion Gap Calculator FAQs
What is an anion gap calculator used for?
An Anion Gap Calculator is used to estimate the anion gap from lab values and help assess electrolyte balance, acid-base balance, and possible metabolic acidosis. It is a clinical aid that supports lab interpretation by highlighting changes in measured ions and unmeasured ions.
What is the normal anion gap range?
The normal range depends on the laboratory and its reference interval. Different methods and instruments can produce different expected values, so the result should always be compared with the range reported on the specific serum chemistry panel.
Why does low albumin affect the anion gap?
Albumin is a major unmeasured anion, so hypoalbuminemia can lower the measured anion gap. That is why an albumin correction or corrected anion gap is often needed to avoid missing an underlying acid-base disorder.
What leads to a high anion gap?
A high anion gap is often linked to lactic acidosis, ketoacidosis, renal failure, and certain toxins. These conditions raise unmeasured anions or limit the body’s ability to maintain acid-base balance.
Should the anion gap be read with other lab results?
Absolutely. The anion gap should always be interpreted with the electrolyte panel, blood gas, albumin, and the rest of the clinical picture. This broader approach improves clinical interpretation and helps distinguish a true metabolic acidosis from other lab patterns.