How the Anion Gap Assesses
The anion gap is a calculated value that helps clinicians evaluate an electrolyte panel and identify hidden sources of acidemia. It reveals the discrepancy between measured cations and measured anions in serum chemistry, mainly using serum sodium, serum chloride, and serum bicarbonate. Because the body maintains electrical neutrality through buffer systems and other charged particles, the gap offers clues about unmeasured anions that may be present in acid-base disorders.
In practical terms, the anion gap acts as a diagnostic tool for distinguishing causes of metabolic acidosis. A widened gap often points to accumulation of acids such as organic acids or other toxins, while a normal gap can suggest bicarbonate loss or impaired acid handling. This renders the anion gap useful in the overall diagnostic approach to systemic illness and metabolic derangement.
Although the number is simple, the meaning is not. The result must be interpreted alongside laboratory values, symptoms, and acid-base status. A calculator can quickly produce a number, but good clinical interpretation depends on whether the patient has true acidemia, whether there Article source is a respiratory component, and whether albumin is altering the expected reference range.
How to Use an Anion Gap Calculator
An anion gap calculator is particularly useful when you already have a new basic metabolic panel or comparable lab set. The calculator usually asks for serum sodium, serum chloride, and serum bicarbonate. Some versions also include albumin so they can report an albumin correction and provide a better corrected value.
To use the tool, input the measured values exactly as reported. The calculator then estimates the difference between major measured ions and displays whether the result falls within the expected range. If albumin is low, the calculator may adjust the output to account for the lower concentration of negatively charged proteins. That correction matters because hypoalbuminemia can make a clinically important gap look deceptively normal.
The calculator is not a diagnosis by itself. It is a quick way to arrange data from the electrolyte panel and aid decision-making. When the output suggests a widened gap, the next step is to check whether the patient has metabolic acidosis on blood gas testing and whether the pattern corresponds to a known cause such as lactic acidosis, ketoacidosis, renal failure, or toxic alcohols.
In a hectic clinical setting, the calculator can also help standardize interpretation across different providers. It turns raw numbers into a structured interpretation guide that supports faster recognition of dangerous acid-base problems.
Anion Gap Calculation and Step-by-Step Calculation
The classic anion gap formula is based on a straightforward difference using tested electrolytes. In its most common form, the calculation is:
anion gap = sodium minus chloride minus bicarbonate
Some references use other formulas, such as sodium minus the sum of chloride and bicarbonate written in a different form, but the principle is the same. The calculation estimates the amount of unmeasured anions in the plasma. Because the body contains many charged particles beyond the routine lab panel, the gap represents an anion deficit in the measured list rather than an actual missing ion.
The following is the stepwise reasoning:
- Begin with serum sodium, which is the dominant measured cation. Deduct serum chloride, the major measured anion. Take away serum bicarbonate, another measured anion related to acid-base balance. Check the remaining value as the estimated anion gap.
If albumin correction is needed, the result is adjusted upward when albumin is low. This can help reveal hidden acid accumulation that might otherwise be masked. The corrected result is often more informative in patients with chronic illness or critical illness, where protein levels can be significantly reduced.
The main advantage anion gap in chronic kidney disease of the formula is simplicity, but its meaning depends on context. A small change in bicarbonate can indicate substantial acid-base disturbance, while a normal number does not automatically exclude serious disease.
Standard Anion Gap vs Increased Anion Gap Acidosis
One major one of the most helpful uses of the anion gap is separating between normal anion gap metabolic acidosis and high anion gap metabolic acidosis. Both are forms of metabolic acidosis, but they differ in mechanism.
In normal anion gap metabolic acidosis, bicarbonate is lost or buffered without a substantial rise in unmeasured acids. The chloride level often rises to maintain electrical balance, so the gap persists within the expected reference range. Frequent clinical scenarios include gastrointestinal bicarbonate loss and certain renal tubular problems, though the exact cause must be evaluated case by case.
In high anion gap metabolic acidosis, the body accumulates acids that are not directly measured by routine chemistry testing. These acids use up bicarbonate and leave behind negatively charged substances, increasing the gap. This pattern is often seen with lactic acidosis, ketoacidosis, renal failure, and ingestion of toxic alcohols.
Understanding the difference helps narrow the diagnostic evaluation. Either pattern can present with low bicarbonate and a low pH, but the gap helps determine whether the issue is primarily bicarbonate loss or accumulation of unmeasured acid. This is why the anion gap remains essential to evaluation of acid-base disorders and systemic acidosis.
Corrected for Albumin Anion Gap
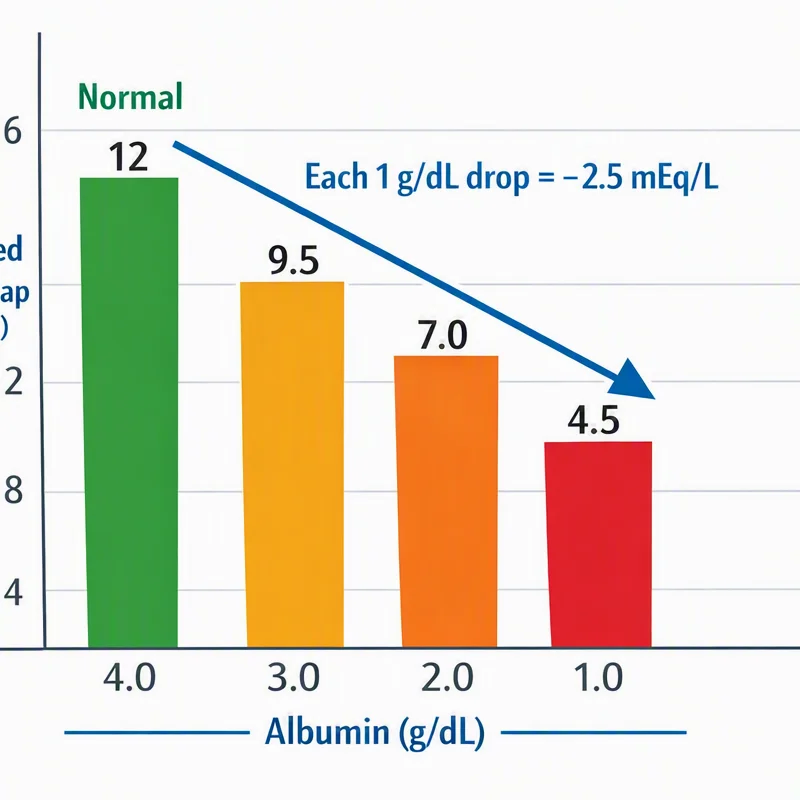
Albumin is one of the major unmeasured anions in blood. When albumin decreases, the anion gap can fall even if significant acids are present. This is why hypoalbuminemia can lead to underrecognition of an elevated gap unless an albumin correction is applied.
The corrected anion gap is particularly important in critical illness, where albumin levels are often low because of inflammation, dilution, or poor nutrition. In these settings, a seemingly normal uncorrected gap may conceal important acid accumulation. The correction helps restore the result closer to its expected physiologic meaning.
Why is this important? Because albumin contributes a substantial portion of the body’s negative charge. When it drops, the measured gap narrows even though the underlying cause of acidemia may not improve. A corrected value gives a better estimate of the true acid burden and improves clinical interpretation.
In practical use, always consider the albumin level before dismissing a borderline result. If the patient has hypoalbuminemia, the corrected gap may shift the case from normal to high and modify the differential diagnosis substantially.
Frequent Causes of Raised Anion Gap Acidemia
When the calculator indicates a higher gap, the next step is to determine the cause of the acidemia. A number of common conditions cause high anion gap metabolic acidosis.
- Lactic acidosis — Often associated with poor perfusion, sepsis, hypoxemia, or severe metabolic stress. Lactate buildup reflects impaired oxygen delivery or altered metabolism. Ketoacidosis — Seen when ketone production rises, such as in diabetic crises, prolonged fasting, or alcohol-related states. Ketones are acidic and contribute to the gap. Renal failure — Reduced kidney function limits acid excretion and allows acidic solutes to accumulate over time. Toxic alcohols — Ingestions such as methanol or ethylene glycol can generate acidic metabolites and cause severe metabolic derangement.
Additional causes may also be considered depending on the case, but these four are among the most frequent and clinically relevant. A widened gap reflects the presence of unmeasured acids, so the task is to ask what acids are likely present and whether the clinical picture fits.
That is why the calculator is best used as part of a larger assessment rather than as a standalone result. The answer should be integrated with history, examination, and complementary labs. In many cases, the anion gap points the clinician toward targeted testing for lactate, ketones, kidney function, or toxic exposures.
How to Read Values in Medical Context
The anion gap is made far more meaningful when interpreted alongside pH and arterial blood gas readings. A patient may have an elevated gap on laboratory testing, but without acidemia on blood gas, the result may be mixed or partially compensated. Likewise, a decreased pH with a normal gap can still signal significant disease.
Ventilatory response matters too. Respiratory compensation is the body’s attempt to lower carbon dioxide and blunt the fall in pH during metabolic acidosis. The relationship between pH, bicarbonate, and carbon dioxide helps determine whether compensation is adequate or whether another process is present.
That is where the delta gap becomes helpful. Delta gap reasoning compares the rise in anion gap with the fall in bicarbonate to detect mixed acid-base disorders. If the gap has increased more than bicarbonate has fallen, there may be an additional metabolic alkalosis. If bicarbonate is lower than expected for the degree of gap elevation, a concurrent normal-gap acidosis may also be present.
This layered analysis is especially helpful in complex illness. A patient with infection, kidney dysfunction, and vomiting may have multiple overlapping acid-base disorders. In those situations, the calculator provides a basis, but the final answer depends on the overall pattern of acid-base disorders.
Interpretation should always be practical: ask whether the patient has a clinically significant metabolic acidosis, whether the respiratory system is compensating appropriately, and whether the gap matches the suspected cause. The calculator helps arrange the numbers, but the diagnosis comes from synthesis.
Challenges and Constraints of Anion Gap Calculation
As with any lab-based tool, the anion gap has constraints. A frequent problem is lab error, which can skew the numbers and yield a misleading result. If the value does not fit the clinical picture, retest and assess specimen quality before drawing conclusions.
A further key limitation is the influence of albumin. Without correction, a low albumin level can mask a widened gap. That means a patient with true acid accumulation may look like they have a normal result if the correction is not considered.
Paraproteinemia is another key issue. Abnormal proteins can disturb the measured chemistry and shift the expected gap. In some cases, these proteins may act as unexpected charged species and mask the usual pattern.
It is also important to remember that the gap reflects unmeasured anions, not a specific disease. A high number tells you that something acidic is accumulating, but it does not identify the cause. The clinician must still evaluate for lactate, ketones, renal dysfunction, and toxins, among other possibilities.
Finally, the normal range is not universal. Different laboratories and methods may use slightly different ranges, so always interpret the result using the local reference range. Small differences in assay design and reporting can affect what is considered normal.
FAQ About Anion Gap and Acidemia Evaluation
What is the anion gap calculator used for?
The anion gap calculator is used to estimate the gap from routine lab values and support evaluation of metabolic acidosis and acidemia. It helps clinicians identify whether the pattern suggests a normal gap or a widened gap and provides a starting point for acid-base interpretation.
What is a normal anion gap range?
The normal range varies by laboratory method, so the result should be compared with the local reference range. In general, a value that falls within the expected range suggests normal anion gap physiology, but clinical context still matters.
Why is it corrected the anion gap for albumin?
You correct for albumin because low albumin decreases the measured gap and can mask a true elevation. Albumin correction enhances detection of acid accumulation, especially in patients with hypoalbuminemia or critical illness.
What leads to a high anion gap in acidemia?
Common causes of a high gap include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. These conditions increase unmeasured anions and often produce high anion gap metabolic acidosis.
Can a normal anion gap still occur with metabolic acidosis?
Yes, it can. Normal anion gap metabolic acidosis is a true form of metabolic acidosis and can occur when bicarbonate is depleted or replaced by chloride. The acid-base picture must be interpreted with pH, arterial blood gas, and the overall clinical context.