What the Anion Gap Measures
The anion gap is a lab-derived metric used to support the assessment of acid-base balance by contrasting the major electrolytes in a blood sample. It is typically calculated from a serum chemistry panel, which includes key values such as sodium, chloride, and bicarbonate. Because these values reflect the body’s charged particles, the result can offer helpful diagnostic support when clinicians are trying to understand a metabolic disturbance.
More specifically, the anion gap estimates the difference between measured positively charged ions and measured negatively charged ions in the blood. That difference reflects the presence of unmeasured anions, which can rise in certain conditions such as metabolic acidosis. This makes the anion gap a practical tool for checking acid-base homeostasis and identifying patterns that may suggest electrolyte imbalance or other systemic issues.
An anion gap calculator makes this process quicker by turning a few lab values into a calculated value that can be reviewed in context. While the calculator does not diagnose disease on its own, it helps organize the information needed for clinical interpretation. In kidney-related evaluation, that can be especially important because the kidneys play a central role in maintaining the body’s buffer system and controlling acid excretion.
Using an Anion Gap Calculator
Employing an anion gap calculator is simple. You enter the lab values for sodium, chloride, and bicarbonate, and in some cases albumin if the tool includes an adjustment. The calculator then uses the formula and returns the result, which can be compared with the expected reference interval or lab results from a specific laboratory.
The basic inputs are commonly taken from a standard blood chemistry report. Sodium is usually the largest measured cation, chloride is a major measured anion, and bicarbonate reflects the blood’s buffering capacity. Albumin is important because it is a major negatively charged protein in the blood and can affect the calculated result when it is low.
To use the calculator accurately, review the exact values from the report rather than estimating them. Small differences in the numbers can affect the final result, particularly when the value is near the cutoff between a normal gap and an increased gap. If the calculator offers an albumin-adjusted result, enter albumin as well to get a more complete picture.
A practical way to think about the process is:
- Input sodium from the serum chemistry panel. Provide chloride from the same panel. Provide bicarbonate from the same panel. Add albumin if the calculator supports albumin-adjusted output. Check the result alongside the rest of the labs and symptoms.
This structured approach supports kidney disease evaluation by helping identify whether the lab pattern fits an acid-base disorder that needs more attention.
Anion Gap Formula and Reference Range
The most common anion gap formula is:
Anion gap = sodium - (chloride + bicarbonate)
Certain labs rely on modified forms of this calculation, and some calculators add potassium or albumin correction. This means, the exact number may differ slightly depending on the method used. The final result is usually reported in mEq/L, a unit that indicates concentration in a way that helps compare electrically charged particles in the blood.
The normal range for anion gap can vary based on the laboratory’s lab reference range. Because methods and measurement platforms differ, one lab may define a normal result differently from another. This is why the result should always be interpreted against the specific reference interval provided with the test report.
In general, a above-normal value may suggest an accumulation of unmeasured acids, while a lower-than-expected value may point to issues such as low albumin or certain measurement differences. The calculator offers a helpful starting point, but the number alone does not tell the full story.
When reviewing results, it is useful to remember that the anion gap is not a stand-alone diagnosis. It is a calculated value that helps narrow the possibilities and guide more focused medical evaluation. In that sense, it is best viewed as a screening and interpretation tool rather than a final answer.
The reason the Anion Gap Is Significant in Kidney Function
The relationship between kidney function and anion gap levels is important in practice because the kidneys manage acid removal and bicarbonate balance. When kidney performance declines, acids may build up in the body, heightening the risk of metabolic acidosis. This is a major reason the anion gap is often included in kidney disease evaluation and broader metabolic workups.
In chronic kidney disease, the kidneys may no longer be able to excrete acid effectively or regenerate enough bicarbonate. As a result, the blood can become more acidic over time. In more advanced renal failure, the buildup of retained acids may produce a higher anion gap and raise the suspicion of uremia, a condition associated with the accumulation of waste products in the blood.
The anion gap can also help distinguish the type of acid-base problem present. Some kidney-related disorders lead to a high gap, while others cause a normal gap acidosis. That distinction is important because it can point toward different mechanisms, such as acid retention, bicarbonate loss, or impaired tubular handling of electrolytes.
For people with known kidney disease, the calculator can be a helpful way to review whether the chemistry panel suggests worsening renal impairment or a new metabolic disturbance. Still, it should always be reviewed with the rest of the clinical picture, including hydration status, medications, and the trend in prior blood tests.
Typical Causes of a High Anion Gap
An elevated anion gap typically indicates there are extra acids in the blood above the usual measured range. This creates an elevated gap and may signal a major metabolic issue. Several frequent causes are particularly important when assessing acid-base balance and kidney function.
Lactic acid accumulation is an important cause. It occurs when lactate accumulates, often due to inadequate oxygen supply, shock, infection, or other systemic stress. Because lactate is an unmeasured anion, it can push the gap higher significantly.
Ketone-related acidosis is another important cause. It can occur when the body produces high levels of ketones, often in uncontrolled diabetes, starvation states, or alcohol-related metabolic changes. These ketones contribute to systemic acidosis and increase the anion gap.
Kidney-related acid retention from advanced kidney dysfunction can also raise the gap. As the kidneys lose the ability to clear metabolic acids, unmeasured anions collect. This is a key reason the anion gap is useful in severe kidney dysfunction and chronic kidney disease.
Alcohol toxins are another serious consideration in a high-gap pattern. Ingestion of substances such as methanol or ethylene glycol can cause dangerous acid buildup and requires urgent medical attention. In these cases, the calculator may assist in spotting an abnormal pattern, but it cannot determine the exact toxin.
To summarize, a high result may point toward one of several metabolic problems:
- lactic acidosis ketone-related acidosis kidney-related acid retention toxic alcohols
The value should be treated as a clue that guides additional testing and clinical interpretation.
Frequent Reasons of a Normal Anion Gap
A typical anion gap does not always mean all is well. It can still be seen in serious acid-base disorders, especially when bicarbonate is lost and chloride rises to compensate. This is often called hyperchloremic acidosis, a pattern in which the anion gap stays normal even though acid-base balance is altered.
Diarrhea is a well-known cause because the body can lose bicarbonate through the gastrointestinal tract. That bicarbonate loss decreases buffering capacity and may produce acidosis without creating extra unmeasured anions. In this setting, chloride often rises to keep electrical balance.
Renal tubular acidosis is another important cause. This kidney-related disorder develops when the renal tubules do not handle acid and bicarbonate properly. Even though kidney function may not be globally failing, the tubular defect leads to a normal gap acidosis pattern that can be detected through careful lab analysis.
These conditions show why the anion gap should be considered alongside other electrolytes and symptoms. A normal value does not exclude disease. It merely suggests that the cause of acidosis may be different from the one seen in high-gap states.
Albumin Adjustment and Why It Matters
Albumin strongly affects the anion gap because it is a negative-charged protein that contributes to the body’s overall charge balance. When albumin is low, the measured anion gap may appear falsely lower than it truly is. This is why hypoalbuminemia can obscure an important acid-base disorder.
To account for that effect, clinicians may use a corrected anion gap. This albumin correction refines the calculated value so that low albumin does not conceal an underlying increase in unmeasured anions. The result is often more informative when evaluating patients with chronic illness, inflammation, malnutrition, or kidney disease.
An albumin-adjusted result can be highly valuable because low albumin is common in people with reduced kidney function or systemic illness. If the uncorrected number looks normal but the albumin is low, the corrected value may reveal a clinically important increase in the gap. That difference can change the interpretation of the lab-derived metric entirely.
In practical terms, albumin correction increases the accuracy of the calculator and supports better medical interpretation. It helps separate a truly normal result from one that only appears normal because the protein level is reduced.
How to Interpret Results in Situation
The anion gap result should never be read in separation. The number becomes relevant when combined with blood tests, clinical context, and the person’s current symptoms. This is especially true when evaluating possible acid-base disturbance or renal metabolic disturbance.
For example, if a person has nausea, rapid breathing, confusion, or weakness, an abnormal gap may point to a more urgent concern. If the same result appears in someone with stable health and no symptoms, the interpretation may CKD metabolic acidosis anion gap be other. The calculator provides a computed value, but the clinician determines what that value means within the overall picture.
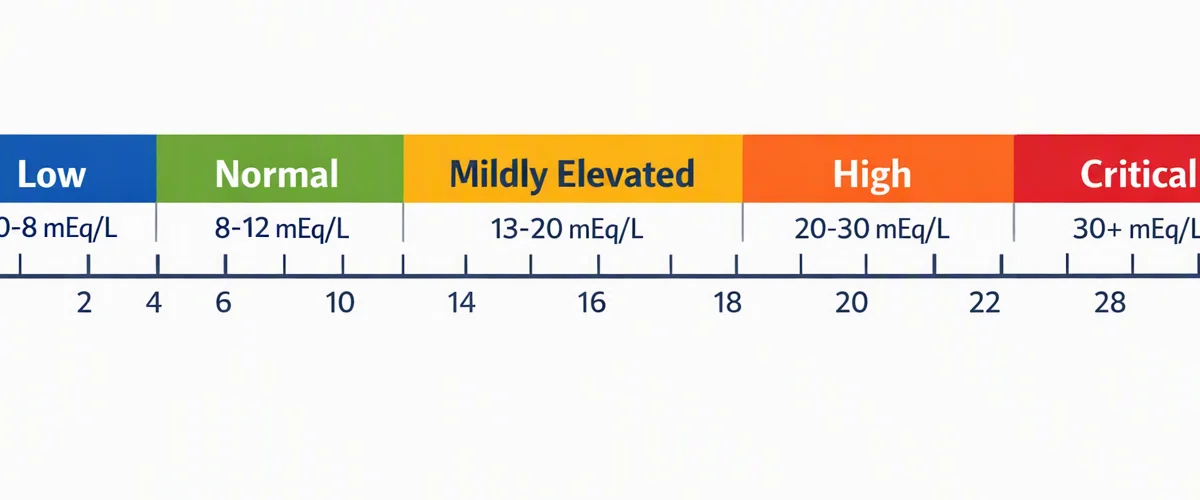
It also helps to review related findings such as creatinine, blood urea nitrogen, glucose, lactate, ketones, and chloride trends. Those values can clarify whether the abnormality reflects kidney performance decline, a systemic acid load, or a separate metabolic issue. This broader review is a core part of effective medical interpretation.
In many cases, the anion gap is just one piece of a larger diagnostic puzzle. It can point toward the presence of systemic acidosis, but additional testing is often needed to identify the underlying cause and determine the appropriate next steps.
Constraints of an Anion Gap Calculator
Even a good anion gap calculator has constraints. The result is only as accurate as the numbers entered, and measurement inaccuracy can affect the output. Small differences in sodium, chloride, or bicarbonate may change the calculated result enough to alter interpretation, especially when values are near the cutoff.
Lab variability is another concern. Different laboratories may use different analyzers, reporting methods, and calculation approaches. That means one lab’s reference intervals may not match another’s. A result that seems abnormal in one setting may fall within the expected range in another.
For this reason, the calculator should be used to assist, not as the sole basis for decision-making. The number is a calculated value, not a literal measurement. It can point to patterns, but it cannot identify the cause of a disorder by itself.
There are instances where the gap may be misleading. Reduced albumin, unusual proteins, or testing issues can obscure the true picture. That is why prudent clinical interpretation remains essential, especially when symptoms or kidney function tests do not match the calculator result.
When to Seek Medical Evaluation
You should seek medical evaluation if an abnormal anion gap appears along with serious symptoms or signs of illness that could reflect a serious acid-base problem. These may include fast breathing, vomiting, confusion, chest pain, marked weakness, or dehydration. A sudden change in how you feel can matter as much as the number itself.
Individuals with established kidney disease or worsening renal impairment should also review abnormal results with a clinician. A nephrologist may be especially helpful if the abnormality is persistent, unexplained, or tied to chronic kidney disease. Kidney-related acidosis can require targeted treatment and close follow-up.
If the result is significantly abnormal and symptoms are progressing, urgent care or emergency evaluation may be appropriate. This is particularly important when the pattern suggests lactic acidosis, ketoacidosis, toxic alcohol exposure, or advanced uremia. A calculator can highlight risk, but it cannot replace direct care when symptoms are concerning.
In short, the anion gap is a valuable support tool for kidney function assessment, but it works best as part of a broader medical review. Persistent abnormalities deserve professional attention.
FAQs About Anion Gap and Kidney Assessment
What is an anion gap calculator used for?
An anion gap calculator is used to calculate the anion gap from lab values such as sodium, chloride, and bicarbonate. It helps assess electrolytes, support kidney function review, and identify possible metabolic acidosis or other acid-base problems. It is a helpful tool for organizing lab results, but it does not replace medical evaluation.
How does anion gap relate to kidney function?
The anion gap connects with kidney function because the kidneys assist with regulating acid removal and bicarbonate balance. As soon as kidney function declines, acids can build up and lead to metabolic acidosis. This can cause an increased gap, especially in chronic kidney disease, renal failure, or uremia.
What is a normal anion gap range?
The normal range depends on the laboratory’s lab reference range and the method used. Results are typically reported in mEq/L. Because different labs use different analyzers and reference intervals, you should compare the result with the range printed on the report rather than relying on a single universal cutoff.
Why should albumin be used to correct the anion gap?
Albumin needs to be used in analysis because low levels can decrease the measured gap and hide a real abnormality. In hypoalbuminemia, a corrected anion gap or albumin adjustment provides a better picture of the real acid-base status. This is especially useful when assessing chronic illness or kidney disease, where albumin may be reduced.
Can a normal anion gap still mean a kidney problem?
Indeed. A standard gap can still arise with kidney-associated issues such as renal tubular acidosis or initial acid base disturbances that do not yet produce a raised gap. It can also appear in hyperchloremic acidosis caused by bicarbonate loss. So a normal result does not rule out kidney disease; it just suggests a distinct pattern that calls for clinical assessment.