What an Anion Gap Calculator Calculates
An anion gap is a simple way to evaluate acid-base balance using standard electrolytes. An anion gap calculator helps you calculate anion gap from standard lab values, usually sodium, chloride, and bicarbonate. In numerous settings, this acts as a helpful diagnostic tool for spotting a hidden metabolic disturbance and informing the next step in lab interpretation.
The concept is basic: measured positive ions and measured negative ions do not fully account for all charged particles in the blood. The “gap” represents unmeasured ions, and changes in that gap can provide meaningful clinical significance. A high value often points to an acid buildup state, while a low value may suggest protein-related changes or lab issues. Used well, the calculator is a screening metric that supports broader acid-base evaluation.
Because the result depends on routine serum electrolytes, it can be checked easily from a basic metabolic panel. That makes it valuable for a quick assessment when a patient has symptoms or labs that suggest acid-base disorders. The result should always be interpreted in context, not in isolation.
How to Compute the Anion Gap
The standard anion gap formula applies the recorded ions in the blood. Most commonly, it is determined as:
Anion gap = sodium - (chloride + bicarbonate)
Some clinicians also include potassium in the calculation, though many laboratories and bedside tools omit it because the difference is usually small. Whether potassium is used depends on the method delta delta calculation example and the lab convention. The key point is to know which version your result reflects before you interpret results.
The values originate from a basic metabolic panel, which provides a quick snapshot of major electrolytes. The panel typically includes sodium, chloride, bicarbonate, and sometimes potassium. Since these results are widely available, the anion gap calculator works well as a rapid clinical interpretation aid when reviewing a patient’s electrolyte panel.
For example, if sodium is 140, chloride is 102, and bicarbonate is 24, the anion gap is 14. That number alone is not the diagnosis, but it is a meaningful clue. A structured way to use the calculator is to:
- Examine the basic metabolic panel for the major electrolytes. Verify the units and calculation method used by the lab. Determine whether potassium is included. Compare the result with the lab’s reference range. Consider whether the pattern suggests a metabolic acidosis or another acid-base disorder.
In practice, the calculator is most valuable when used as part of a larger clinical picture rather than as a standalone number.
Expected Anion Gap Range and Assessment
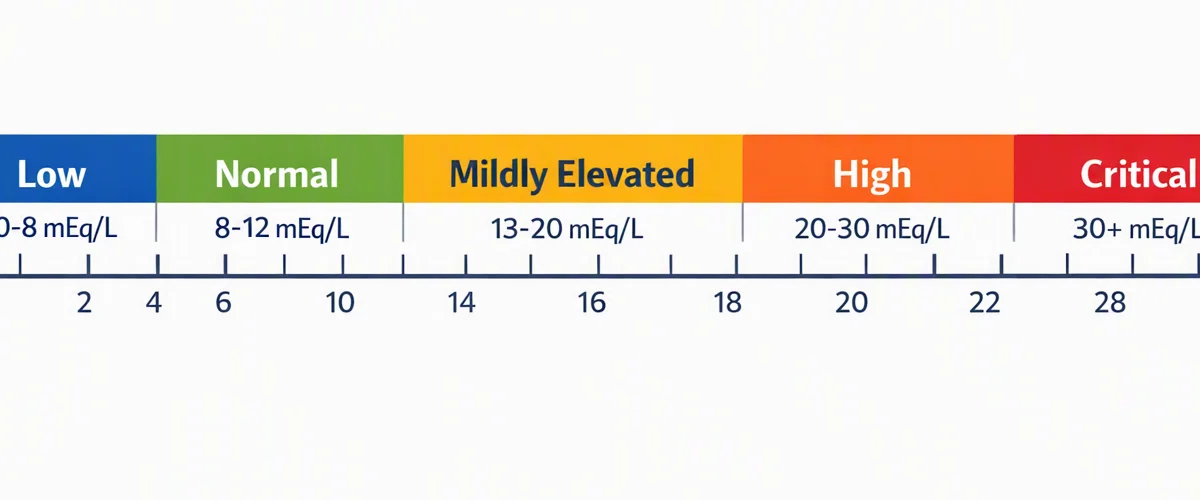
The reference range for the anion gap varies with the lab method and the reference range reported by the facility. Different analyzers, different electrolyte measurement techniques, and different inclusion of potassium can all alter the expected value. That is why the number should always be matched to the specific laboratory’s reference interval.
A normal anion gap does not automatically mean everything is fine, and an abnormal gap does not automatically mean one specific diagnosis. Instead, the number points to the type of metabolic acidosis or other acid-base disorders present. A normal gap with acidosis often points toward bicarbonate loss or chloride retention, while an elevated gap suggests unmeasured acids have accumulated.
Albumin matters because it is a major unmeasured anion. When serum albumin is low, the measured anion gap may appear falsely normal or only mildly elevated even when clinically important acid accumulation is present. That is why the raw number must be judged alongside the patient’s albumin level and overall presentation.
As a practical rule, if the clinical picture suggests acidosis but the anion gap is not clearly elevated, consider whether reduced albumin is masking the result. This is where the corrected value becomes useful. The calculator is most helpful when it supports a careful review of acid-base imbalances rather than replacing that review.
Typical Causes of an Elevated Anion Gap
An elevated anion gap often indicates high anion gap metabolic acidosis. This implies the body has collected acids that are not fully reflected in the routine electrolyte measurements. Spotting this pattern early can focus the differential and direct the next steps in evaluation.
Typical causes include:
- Lactic acidosis, which can occur when tissues are not well supplied with blood or when lactate production increases. Ketoacidosis, seen with diabetic ketoacidosis, starvation, or alcohol-related ketosis. Renal failure, where impaired acid excretion allows organic acids to build up. Toxic alcohols, which can produce dangerous metabolic derangements and require urgent attention.
Lactic acidosis is a classic cause of a high anion gap and should be considered when there is circulatory collapse, hypoxia, infection, or severe physiologic stress. Ketoacidosis is another frequent cause, especially when glucose, ketones, and volume status support that diagnosis. Renal failure can contribute by reducing the body’s ability to clear acids, and toxic alcohols may create a particularly serious and time-sensitive presentation.
A high result should prompt a focused review of symptoms, medications, toxic exposures, hemodynamic status, glucose, lactate, kidney function, and ketones. The anion gap calculator helps identify the pattern, but the cause still requires clinical correlation.
Common Causes of a Normal-Gap Metabolic Acidosis
A normal gap does not rule out acidosis. In normal anion gap metabolic acidosis, bicarbonate is lowered but chloride increases to maintain electrical balance. This pattern is also called hyperchloremic acidosis because of the associated hyperchloremia.
Frequent causes include diarrhea, renal tubular acidosis, and other conditions that lead to bicarbonate loss. These disorders typically do not elevate unmeasured acids the way high-gap states do, so the anion gap may stay in the usual reference range.
Diarrhea can cause major gastrointestinal loss of bicarbonate. Renal tubular acidosis reflects impaired renal handling of acid or bicarbonate and often presents with a normal anion gap and abnormal urine studies. In both cases, the pattern may be forgotten if the anion gap calculator is used without a broader acid-base review.
When the result suggests normal-gap acidosis, think about:
- Persistent gastrointestinal bicarbonate loss Renal acidification problems such as renal tubular acidosis Hyperchloremia from fluid administration or salt retention Medication effects and mixed disorders
This is where careful lab interpretation matters. The anion gap is a clue, not the full answer.
Correcting Albumin and Why It Is Important
Serum albumin is one of the most important factors affecting the anion gap. Since albumin carries negative charge, low levels can decrease the measured gap even when clinically significant acids are present. This is why hypoalbuminemia can conceal a real problem.
Albumin correction calibrates the measured value to calculate what the gap would be if albumin were normal. The result is the corrected anion gap. This is especially important in patients with severe illness, malnutrition, liver disease, inflammation, or fluid shifts, where hypoalbuminemia is often seen.
Using the corrected value improves recognition of acid-base disorders and limits false reassurance. A normal-appearing gap in a patient with low albumin may still reflect an underlying high anion gap metabolic acidosis. In other words, the correction can uncover hidden acid accumulation that the raw number misses.
To use albumin correction well, remember these three points:
- Low albumin reduces the uncorrected anion gap. The corrected anion gap more closely shows true acid burden. Correction enhances the accuracy of clinical interpretation in complex cases.
For a quick assessment, the calculator is still useful without correction, but correct for albumin whenever the result and the clinical picture do not match.
Using the Calculator in a Clinical Setting
The most effective way to use an anion gap calculator is as part of a real-time review of the patient’s complaints, exam, and test results. First review the electrolyte panel or basic metabolic panel, then pair the result with a blood gas when available. anion gap in chronic kidney disease This method helps determine whether there is true acidemia and whether compensation is appropriate.
If a blood gas or arterial blood gas is available, it can verify the acid-base status and show whether the patient has respiratory compensation or a mixed problem. The gap then becomes one piece of a larger puzzle. It is especially helpful in evaluating a suspected metabolic disturbance when symptoms are vague, such as weakness, confusion, nausea, or rapid breathing.
Clinically, the most useful workflow is:
- Assess the electrolyte panel and calculate the gap. Inspect the blood gas or arterial blood gas for pH and ventilation status. Assess whether the result fits metabolic acidosis or another disorder. Look for likely possible causes such as lactate, ketones, kidney dysfunction, or toxin exposure. Leverage the result to direct the diagnostic workup.
This becomes the calculator has real value as a diagnostic tool. It can promptly highlight abnormalities, support clinical interpretation, and help prioritize urgent evaluation.
Constraints, Problems, and When to Get Further Evaluation
Even a well-used anion gap calculator has significant limitations. A standard or unexpected result can be inaccurate if the underlying electrolyte values are wrong, if the sample is compromised, or if the patient has a complex mixed picture. One of the first issues is lab error, which can skew sodium, chloride, or bicarbonate and produce a false result.
A further major issue is the mixed acid-base disorder. A patient may have several process at the same time, such as metabolic acidosis plus respiratory alkalosis, or high-gap acidosis plus a normal-gap process. In these cases, the anion gap alone may not reveal the full picture.
That is why an arterial blood gas can be especially valuable. It explains the pH and ventilation component, while the chemistry panel provides the electrolyte pattern. When the clinical picture is unclear, using both tests together increases accuracy and reduces missed diagnoses.
The anion gap delta can also help spot mixed disorders. If the change in the gap does not match the change in bicarbonate as expected, there may be another metabolic process in addition to the one causing the elevated gap. This is especially important in patients with severe illness or overlapping causes.
Request further evaluation when:
- The result does not fit the symptoms or exam. There is concern for lab error. The patient may have a mixed acid-base disorder. The gap is high and the cause is not obvious. The patient needs urgent assessment for metabolic acidosis or toxin exposure.
When used carefully, the calculator is a helpful screening metric, but it should never replace a full clinical evaluation.
FAQs About the Anion Gap Calculator
What is the anion gap and why does it matter?
The anion gap is a calculated number that reflects the difference between measured positively and negatively charged ions in the blood. It matters because it helps identify metabolic acidosis and other acid-base disorders. As a rapid assessment tool, it can indicate hidden acid accumulation, inform lab interpretation, and support the search for the underlying cause.
How do you calculate the anion gap from lab results?
You typically use the anion gap formula: sodium less the combined chloride and bicarbonate. In some cases, potassium is added, depending on the lab method. The values come from a basic metabolic panel or an electrolyte panel, and the result should be reviewed alongside the lab’s reference interval before you interpret results.
What is considered a normal anion gap?
The normal range changes by lab because methods and measurement conventions differ. Always use the local reference range provided with the report. A number outside that range may suggest a metabolic disturbance, but the result must be interpreted in the context of the patient, the serum electrolytes, and any associated blood gas findings.
Why should the anion gap be corrected for albumin?
The gap should be adjusted because serum albumin is a major unmeasured anion. When albumin is low, the uncorrected value may look normal even when acid is present. Albumin correction gives a corrected anion gap that better reflects the true acid load, especially in patients with hypoalbuminemia and complex acid-base disorders.
What can cause a high or low anion gap?
A high value often suggests high anion gap metabolic acidosis from causes such as lactic acidosis, ketoacidosis, renal failure, or toxic alcohols. A normal-gap acidosis may be due to diarrhea, renal tubular acidosis, hyperchloremia, or bicarbonate loss. A low value can occur with hypoalbuminemia, lab error, or other less common conditions, so it should always be reviewed carefully in context.