What Is the Anion Gap?
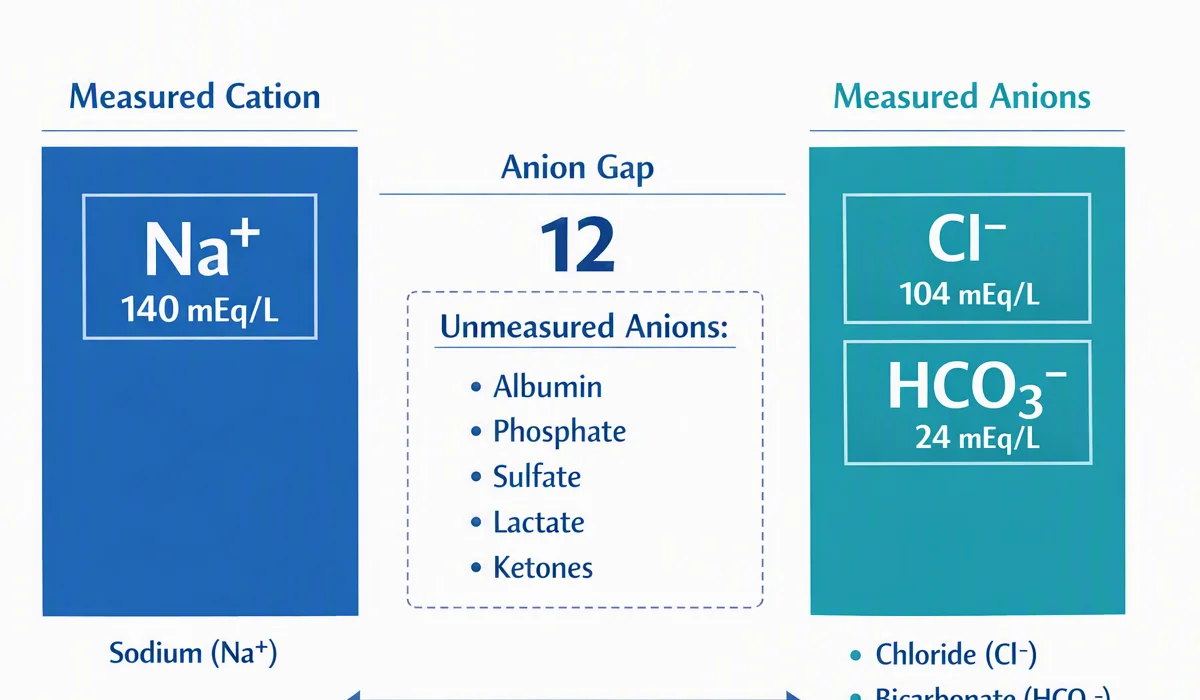
The anion gap is a calculated value that helps doctors assess acid-base balance and recognize causes of metabolic acidosis. It is based on common electrolytes measured on a routine chemistry panel, especially serum sodium and serum chloride, along with bicarbonate. Because not every charged particle is routinely measured, the anion gap approximates the amount of unmeasured anions in the blood.
In basic terms, the anion gap is a lab clue. A normal result suggests that the major measured ions are balanced in the expected range, while an elevated anion gap points toward an accumulation of acids or other negatively charged substances. This makes it an important diagnostic marker in a broad range of conditions, including diabetic emergencies.
The logic behind the calculation is clear. Sodium is the main measured positive ion, while chloride and bicarbonate are major measured negative ions. When the difference between them shifts, it can reflect alterations in serum chemistry caused by acid accumulation, loss of bicarbonate, or both. That is why the anion gap is closely tied to buffer systems and the body’s ability to maintain pH.
Although the formula may vary slightly by laboratory, the idea is the same: the anion gap is a practical way to detect hidden acid load. This is especially useful during clinical assessment, when symptoms and labs must be interpreted together rather than in isolation.
What Occurs to the Anion Gap in Diabetic Ketoacidosis?
Diabetic ketoacidosis typically produces a high anion gap metabolic acidosis. In DKA, the body produces excess ketone bodies, including beta-hydroxybutyrate and acetoacetate, which act as acids. As these acids increase, bicarbonate is consumed, and the anion gap widens because the negatively charged ketoacids are not fully reflected in standard lab measurements.
This is why DKA is a classic cause of high anion gap metabolic acidosis. The lab pattern often reveals low serum bicarbonate, elevated ketones, hyperglycemia, and an increased gap that suggests acid accumulation. In other words, the body is in an acidotic state because it cannot process glucose properly and instead transitions into uncontrolled fat metabolism.
When DKA progresses, the acid load becomes more pronounced and the laboratory picture often becomes clear. The combination of ketosis and bicarbonate depletion creates a metabolic derangement that can be followed through serial blood testing. Because the anion gap varies to changing levels of unmeasured acids, it works as a useful marker during diagnosis and treatment monitoring.
One important point is that the anion gap does not directly assess ketones directly. Instead, it shows the effect of those ketones on acid-base balance. That means a rising gap can signal worsening ketoacidosis even before all symptoms fully evolve, especially when interpreted alongside serum bicarbonate and blood gas analysis.
What Causes DKA Raise the Anion Gap?
The key reason DKA elevates the anion gap is insulin deficiency. When there is not enough insulin, glucose does not enter cells effectively, so the body acts like it is starving despite high blood sugar. This starts lipolysis, a process in which fat stores are broken down into free fatty acids that move to the liver.
In the liver, these free fatty acids are converted into ketone bodies, especially beta-hydroxybutyrate and acetoacetate. These molecules are acids, and as they accumulate, they increase acid load in the blood. The result is a fall in bicarbonate and a rise in unmeasured anions, which causes the anion gap upward.
This process is part of a larger chain reaction:
- Insulin shortage leads to uncontrolled fat breakdown. Lipolysis frees free fatty acids into circulation. The liver converts those fats into ketone bodies. Ketone bodies promote acid accumulation. Bicarbonate is consumed as the body attempts to buffer the acid. The anion gap rises because of the additional unmeasured anions.
In practice, this is why DKA is such a strong example of acid-base imbalance. The body’s buffer systems are overwhelmed, and the lab pattern mirrors the underlying chemistry. The anion gap is not just a number; it is a clue that the patient has a significant metabolic problem requiring urgent evaluation.
Among the ketone bodies, beta-hydroxybutyrate is especially important because it is often the leading ketoacid in DKA. Acetoacetate is also involved, but the relative balance can shift with disease severity and treatment. That is one reason why serum ketone testing and blood gas analysis can add context to the anion gap calculation.
How to Interpret Anion Gap in DKA Lab Results
Interpreting the anion gap in DKA requires looking at the entire pattern, not just one result. The most helpful labs usually consist of serum bicarbonate, glucose, electrolytes, and either an arterial blood gas or venous blood gas. Collectively, these values show whether the patient has metabolic acidosis and how severe it is.
Low serum bicarbonate is a key clue. In DKA, bicarbonate drops because it is consumed while buffering ketoacids. A low bicarbonate level with an elevated anion gap strongly suggests a high anion gap metabolic acidosis, especially when hyperglycemia and ketosis are present.
Blood gas analysis helps confirm the acid-base disorder. An arterial blood gas can show the degree of acidemia and respiratory compensation, while a venous blood gas is often sufficient for many clinical settings and can provide nearly the same acid-base information. Either way, the blood gas helps clinicians understand whether the patient is in a significant acidotic state or partially compensating.
Lab interpretation should also consider the broader clinical picture. Symptoms such as nausea, vomiting, abdominal pain, Kussmaul breathing, weakness, and dehydration may all support the diagnosis. The anion gap is one piece of the puzzle, but in DKA it is a very useful diagnostic marker for tracking metabolic derangement.
Because treatment changes the chemistry quickly, serial testing matters. Rising bicarbonate and falling ketone levels usually indicate improvement. If the gap remains elevated, clinicians may look for ongoing acid production or another cause of metabolic acidosis. This is where careful differential diagnosis becomes critical.
How an Anion Gap Calculator Helps
An Anion Gap Calculator makes easier anion gap calculation and minimizes math errors during busy care. It takes lab values such as serum sodium, serum chloride, and serum bicarbonate to determine the gap promptly. That makes it it especially useful for prompt lab interpretation when a patient may be critically ill.
A calculator can also assist with a corrected anion gap when albumin is low. Since albumin is a major unmeasured anion, hypoalbuminemia can make the anion gap appear falsely normal or less elevated than expected. Adjusting for albumin gives a more accurate view of the patient’s acid-base status.
This becomes important in DKA because not all patients present with the same baseline protein levels or hydration status. If albumin is low, an uncorrected value may underestimate the severity of the acid load. A corrected anion gap can therefore strengthen clinical assessment and help identify hidden metabolic acidosis.
An Anion Gap Calculator is also useful during treatment monitoring. As fluids and insulin are started, bicarbonate may rise and ketones may fall. Tracking the gap over time can show anion gap in chronic kidney disease whether the acidotic state is improving. That renders the tool useful not only at diagnosis but also throughout management.
In short, the calculator turns serum chemistry into actionable insight. It supports faster anion gap calculation, better recognition of unmeasured anions, and clearer interpretation of changing lab values in DKA.
Can DKA Have a Normal Anion Gap?
Yes, diabetic ketoacidosis can at times present with a normal anion gap metabolic acidosis, especially during the treatment phase. This may happen after the initial ketoacidosis has improved but bicarbonate has not fully recovered, or when the chemistry shifts because of fluid therapy.
One frequent reason is saline infusion. Large amounts of normal saline can increase serum chloride, which leads to a chloride shift and can produce a normal anion gap metabolic acidosis or a non-anion-gap pattern. In this situation, the original ketoacidosis may be resolving, but the lab picture can look different from the initial presentation.
That does not mean the DKA has disappeared completely or that the patient is fully recovered. Instead, it shows how treatment can change the laboratory pattern. The chloride level rises relative to bicarbonate, and the gap may narrow even while careful monitoring is still needed.
This is why serial assessment is important. Clinicians often look at glucose, ketones, serum bicarbonate, and the corrected anion gap together to understand the full trajectory. A normal gap later in treatment may suggest a transition from high anion gap metabolic acidosis to normal anion gap metabolic acidosis rather than complete resolution.
Recognizing this shift helps avoid misinterpretation. The patient may still need ongoing treatment, and the lab pattern should be viewed in the context of the overall clinical assessment.
What Other Conditions Can Mimic DKA?
A number of conditions can mimic DKA since they also lead to an elevated anion gap and metabolic acidosis. That is why differential diagnosis matters. A high gap is only a clue, not a definitive answer.
Lactic acidosis is one major mimic. It develops when lactate accumulates from poor tissue perfusion, severe illness, seizures, or other stressors. Like DKA, it can produce a high anion gap and low serum bicarbonate. Blood gas analysis and the clinical context help separate it from ketoacidosis.
Kidney failure is another key cause. When the kidneys cannot remove acids effectively, unmeasured anions accumulate and metabolic acidosis develops. In some cases, renal failure and DKA can happen together, which Learn more makes the laboratory picture more complex.
Toxic alcohols such as methanol, ethylene glycol, and related exposures can also lead to severe high anion gap metabolic acidosis. These emergencies may need specialized testing and urgent treatment. The history, osmolar gap, and supporting laboratory findings can help distinguish them from DKA.
Starvation ketosis can look like mild DKA because it also involves ketone production. However, it is usually linked to less severe hyperglycemia and a different clinical setting. Although ketosis may be present, the amount of acid accumulation is often less dramatic than in diabetic ketoacidosis.
Other look-alikes may include mixed disorders, medication effects, and other causes of metabolic imbalance. That is why the anion gap should always be interpreted alongside serum chemistry, glucose, ketones, and blood gas analysis. Careful interpretation helps prevent missing another diagnosis.
When You Should Seek Immediate Medical Attention
Diabetic ketoacidosis is a medical emergency. Seek urgent medical care if there is marked hyperglycemia, marked dehydration, vomiting, deep or rapid breathing, confusion, or altered mental status. Such findings may indicate a critical acidotic state that requires immediate evaluation.
Prompt management is needed because diabetic ketoacidosis can progress quickly and affect several organ systems. The combination of insulin deficiency, dehydration, electrolyte imbalance, and acid accumulation can become potentially fatal without prompt care. In many cases, treatment includes fluids, insulin, electrolyte replacement, and close monitoring of acid-base balance.
Do not wait for symptoms to worsen if diabetic ketoacidosis is suspected. A patient with hyperglycemia, ketone bodies in the blood or urine, and an elevated anion gap needs urgent medical attention. The same is true if marked weakness, confusion, or signs of shock appear.
Because the condition can change quickly, treatment should be guided by serial lab interpretation and clinical assessment. Anion gap trends, serum bicarbonate, and blood gas results all help show whether the metabolic acidosis is improving or whether emergency treatment must continue.
FAQ
Why does diabetic ketoacidosis cause a high anion gap?
Diabetic ketoacidosis causes a high anion gap because insulin deficiency triggers lipolysis, which increases free fatty acids and leads to production of ketone bodies such as beta-hydroxybutyrate and acetoacetate. These acids accumulate, bicarbonate is consumed, and unmeasured anions rise, creating high anion gap metabolic acidosis.
Can the anion gap be normal in diabetic ketoacidosis?
Yes. The anion gap can become normal during the treatment phase, especially after saline infusion increases chloride and creates a chloride shift. This may produce a normal anion gap metabolic acidosis even as the patient is recovering from the initial ketoacidosis.
What laboratory values are necessary for an Anion Gap Calculator?
An Anion Gap Calculator typically needs serum sodium, serum chloride, and serum bicarbonate. Albumin may also be needed to calculate a corrected anion gap, especially if the patient has low albumin or another condition that could affect the result.
How does albumin affect the anion gap result?
Albumin is a major uncounted anion, so low albumin can make the anion gap appear decreased than it truly is. A corrected anion gap compensates for this effect and gives a more reliable view of metabolic acidosis and acid accumulation.
What other conditions can cause a high anion gap besides DKA?
Other causes include lactic acidosis, renal failure, toxic alcohols, and starvation ketosis. These conditions can also produce elevated anion gap values, so differential diagnosis and blood gas analysis are important for proper lab interpretation.