What’s the Delta Gap?
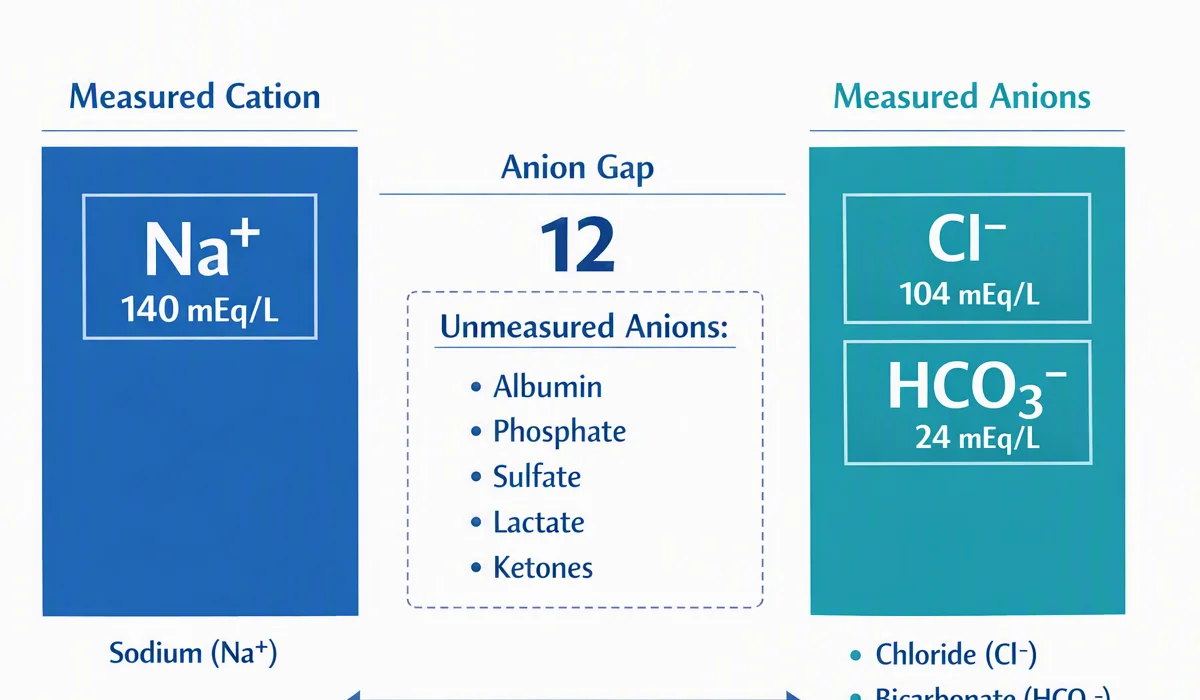
The delta gap is a tool used in acid-base analysis to reveal whether a patient with an abnormal anion gap also has another hidden acid-base disorder. It is especially useful in metabolic acidemia, where the main question is not only whether the anion gap is high, but also whether the change in the gap matches the change in bicarbonate level.
In practical terms, the delta gap matches up the rise in the anion gap with the fall in bicarbonate. This comparison helps identify a possible mixed disorder. If the numbers do not move together as expected, there may be a second process such as concurrent metabolic alkalosis or a hyperchloremic metabolic acidosis.
You may also hear the term delta-delta. That refers to the same idea: comparing the difference between the measured abnormality and the expected change. A well-designed anion gap calculator can make this process easier by arranging the laboratory values and helping you quickly work out delta gap at the bedside or during review of a blood gas.
Calculating Delta Gap in Simple Steps
To correctly use an anion gap calculator properly, start with the core formula for anion gap and then contrast the result with the bicarbonate change. The process is straightforward, but accuracy depends on using the right serum electrolytes and checking whether albumin correction is needed.
Below is the typical step-by-step formula workflow:
- 1. Check serum sodium, serum chloride, and serum bicarbonate. 2. Determine the anion gap: sodium minus chloride minus bicarbonate. 3. Compare the measured anion gap to the expected normal range. 4. Subtract the normal anion gap from the measured anion gap to get the gap difference. 5. Relate that gap difference with the drop in bicarbonate.
That comparison is the essence of delta-delta analysis. The expected change in bicarbonate should usually track the rise in the anion gap. When it does not, the result suggests something beyond a simple high gap acidosis.
In simple terms: the anion gap calculation indicates whether unmeasured acids are accumulating, while the delta gap tells you whether the acid-base shift is isolated or part of a mixed disorder detection process. An anion gap calculator helps keep the arithmetic consistent, especially when evaluating multiple electrolytes or doing rapid diagnostic support.
Formula for Delta Gap and Normal Ranges
The delta gap relies on a comparison between the measured anion gap and the normal anion gap. The usual formula is:
Delta gap = Measured anion gap - Normal anion gap
Afterward compare it to the bicarbonate deficit:
Delta ratio = Delta gap / (Normal bicarbonate - Measured bicarbonate)
Some clinicians focus on the delta ratio, while others use the delta gap to identify a mismatch between the rise in anion gap and the fall in bicarbonate. Both approaches help with clinical interpretation of metabolic acidosis.
Usual reference points include:
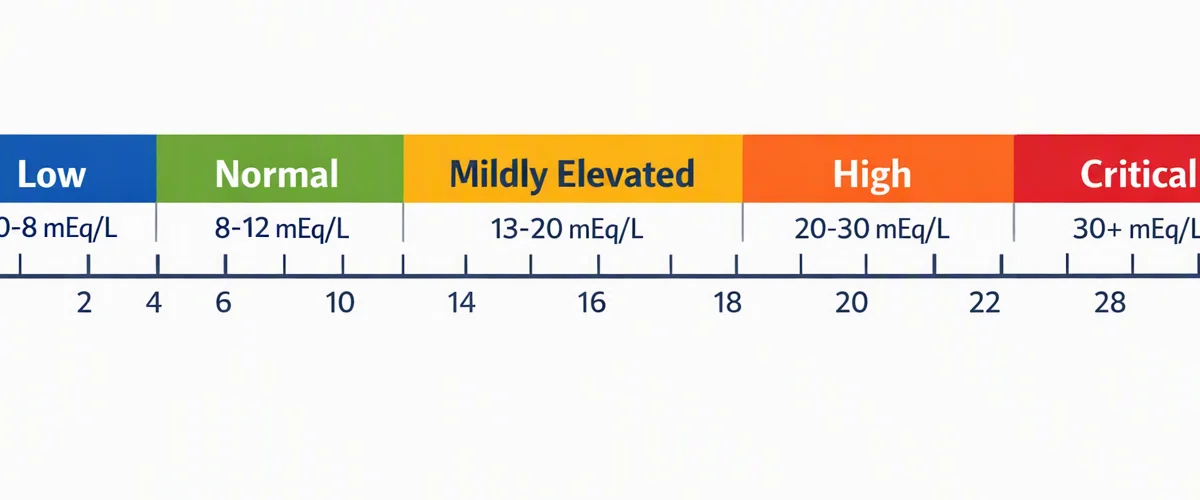
- Normal anion gap: commonly about 8 to 12 mEq/L, depending on the lab Bicarbonate: typically around 22 to 26 mEq/L Albumin: reduced albumin can decrease the apparent anion gap
As albumin correction matters, a low albumin level can conceal a true high anion gap metabolic acidosis. Albumin is a major unmeasured anion, so if it is reduced, the measured anion gap may seem normal when it is not. That is why the best anion gap calculator tools often consider albumin adjustment when available.
During acid-base analysis, normal ranges are not just numbers to memorize. They are part of the workflow used to https://anion-gap-app508.raidersfanteamshop.com/which-are-the-signs-of-a-reduced-anion-gap interpret serum bicarbonate alongside sodium concentration and chloride concentration. Small shifts can reveal major disease processes, and the gap difference can provide clues about the body’s metabolic compensation.
How to Understand Delta Gap Results
Interpreting the delta gap means determining whether the change in bicarbonate aligns with the increase in anion gap. This is the point where the result becomes clinically useful for identifying a mixed acid-base disorder.
Typical patterns of interpretation include:
- If the delta gap and bicarbonate change are approximately proportional, the disorder may be a simple high anion gap metabolic acidosis. When the delta gap is more elevated than expected, there may be an associated metabolic alkalosis or preexisting elevated bicarbonate. If the delta gap is less than expected, there may be a concurrent normal anion gap metabolic acidosis.
For instance, a patient may present with severe metabolic acidosis from a high anion gap process, but the bicarbonate may be even lower than predicted. That difference suggests a second acid-base problem. That is why delta gap analysis is useful for mixed disorder detection rather than simply labeling the case as “acidosis.”
The result should always be interpreted in the context of the blood gas, the patient’s symptoms, and the complete set of electrolytes. A calculator can support the math, but acid-base interpretation still requires clinical judgment. In real-world use, the delta gap often helps explain why the pH, bicarbonate level, and anion gap do not appear to “fit” neatly together.
Once the high anion gap is clearly present, the delta gap helps answer a second question: is another process also occurring? That answer can change management and lead clinicians to search for overlooked causes of bicarbonate loss or alkalosis.

Frequent Causes of Elevated Delta Gap
Abnormal delta gap findings often indicate a known cause of high anion gap metabolic acidosis or a mixed acid-base picture. The main conditions include lactic acidosis, diabetic ketoacidosis, renal failure, and exposure to toxins.
Lactic acidosis increases unmeasured acids and may lead to a substantial rise in the anion gap. If bicarbonate falls more or less than expected, the delta gap may show an additional process. This can happen in shock, sepsis, severe hypoxia, or other states that impair tissue oxygen delivery.
Diabetic ketoacidosis is another common cause. In ketoacidosis, ketone accumulation raises the gap upward, and the bicarbonate usually falls. If vomiting or volume depletion is also present, the delta gap may point to a concurrent metabolic alkalosis, which is important for treatment planning.
Renal failure can also result in accumulation of acids that raise the anion gap. As kidney function declines, acid excretion falls and the acid-base pattern may become more complex. A delta gap calculation can help determine whether the biochemical pattern reflects a single process or a mixed state.
Toxins are another category to review when the anion gap is elevated. Toxic alcohols and other ingestions can cause severe acid-base abnormalities, and the delta gap may help clarify how the bicarbonate response compares with the magnitude of the gap increase.
Because each cause has its own pattern, the delta gap should be read alongside the history, the blood gas, and the measured serum electrolytes. That combination gives the most informative diagnostic support.
Delta Gap vs Anion Gap: How Do They Differ?
This anion gap and the delta gap are related, but they raise different questions. The anion gap is a initial and classification tool. It indicates whether there are extra unmeasured anions in the blood. The delta gap is a deeper check that examines how the bicarbonate change compares with the gap change.
More simply, anion gap calculation tells you whether the patient likely has a high anion gap metabolic acidosis. The delta gap helps assess whether that finding is pure or whether an additional condition is present. This is especially helpful when the clinical picture suggests acid-base balance is not fully explained by the basic numbers.
The delta ratio is closely connected to the delta gap. Some clinicians use it to contrast the size of the gap increase with the size of the bicarbonate drop. A near-expected ratio supports a single process, while a markedly elevated or decreased ratio can point to a mixed acid-base disorder.
The main difference is therefore functional:
- Anion gap: detects abnormal unmeasured anions Delta gap: verifies whether the change pattern fits expectations
For that reason, a well-designed anion gap calculator is useful, but it should not replace thoughtful review of lab values. The best approach is to use the calculator for arithmetic and then bring in clinical reasoning to understand the acid-base analysis.
Example Walkthrough Using an Anion Gap Calculator
Below is a basic calculation example showing how to use an anion gap calculator to calculate delta gap. Assume the following lab values are available:
- Serum sodium: 140 mEq/L Cl: 100 mEq/L Bicarbonate level: 12 mEq/L
To begin, determine the anion gap:
140 - 100 - 12 = 28
If the normal anion gap is 12, then the delta gap is:
28 - 12 = 16
Next, compare this with the bicarbonate deficit. When the normal bicarbonate is 24, then:
24 - 12 = 12
The delta quotient would be:
16 / 12 = 1.33
This finding shows the rise in anion gap is slightly greater than the fall in bicarbonate, which may indicate a pure high gap process or a high gap process with an additional concurrent factor. That is where clinical judgment matters. The pattern should be interpreted with the full blood gas result, symptoms, and other serum electrolytes.
When the patient also had a low albumin level, an correction for albumin might increase the corrected anion gap further, strengthening the evidence for metabolic acidosis. This helps explain why calculator-based review is valuable: it improves consistency when working through a stepwise formula during urgent evaluation.
Common Questions
How do you determine delta gap from an anion gap?
To begin, calculate the anion gap using blood sodium, chloride levels, and bicarbonate levels. Afterward, subtract the normal anion gap from the measured value to get the delta gap. Then, contrast the result with the drop in bicarbonate. This is the core delta gap calculation used in acid-base analysis and can be streamlined with an anion gap calculator.
What can a high delta gap mean?
A high delta gap usually means the increase in anion gap is larger than the fall in bicarbonate would predict. This can point to a mixed acid-base disorder, such as high anion gap acidosis plus metabolic alkalosis or a concurrent non-gap acidosis pattern. It serves as a clue for deeper acid-base interpretation, not a diagnosis by itself.
When do you use a delta gap instead of just the anion gap?
Use the delta gap when the patient has metabolic acidosis and you want to know whether the process is isolated or mixed. The anion gap alone tells you whether a gap is present, but the delta gap helps identify hidden additional disorders. It is especially helpful in high anion gap metabolic acidosis cases where the overall pattern is not fully explained by the basic numbers.
What’s the difference between delta gap and delta ratio?
The delta gap measures the rise in anion gap to the normal value. The delta ratio goes one step further by dividing the delta gap by the bicarbonate deficit. Both are used in acid-base analysis, and both support mixed disorder detection. Many clinicians use them interchangeably in practice, although the ratio is more explicit mathematically.
Can albumin levels affect delta gap interpretation?
Yes. Albumin correction matters because low albumin can make the anion gap appear lower than it really is. If albumin is reduced, the measured anion gap may underestimate the severity of a high anion gap metabolic acidosis. That means albumin should be considered when interpreting delta gap results, especially when using an anion gap calculator for clinical decision support.