What the Anion Gap Measures
anion gap in chronic kidney diseaseThe anion gap is a helpful way to look at the balance of charged particles in the blood, especially when evaluating serum electrolytes and overall acid-base balance. It is not a direct value of a single substance. Instead, it is a derived estimate that shows the difference between commonly measured positive ions and negative ions in a standard chemistry panel.
An anion gap calculator uses routine lab values to estimate how many unmeasured anions may be present in the bloodstream. This makes it a valuable diagnostic aid in the evaluation of acid-base disorders, especially metabolic acidosis. In simple terms, if the gap is higher or lower than expected, it can point to underlying changes in the body’s chemical balance.
The calculation is part of everyday serum chemistry and is commonly derived from an electrolyte panel. It is especially helpful because the result can suggest whether an acid load is present, whether how to calculate anion gap with potassium there may be changes in renal function, or whether additional testing is needed to clarify the cause of an abnormal result. The anion gap is best understood as a indicator, not a final diagnosis.
How to Compute the Anion Gap from Lab Results
The traditional anion gap formula uses three lab values: sodium, chloride, and bicarbonate. Most commonly, the calculation is:
Anion gap = sodium - (chloride + bicarbonate)
This formula measures the dominant measured cation, sodium, against the major measured anions, chloride and bicarbonate. The result shows the amount of unmeasured anions in the blood. Because different laboratories may report slightly different values or use different methods, the exact interpretation should always be tied to the lab’s own reference interval.
To work with an anion gap calculator correctly, enter the values from the same blood draw. Mixing results from different times can distort the clinical interpretation. Also check whether the calculator is using the traditional formula or a version that includes potassium, since that changes the number slightly. Most routine clinical use focuses on the sodium-based version.
Example conceptually: if sodium is 140, chloride is 104, and bicarbonate is 24, the calculation is 140 - (104 + 24) = 12. That result is often considered within a typical range, but the exact normal anion gap depends on the lab method and the reporting system.
Anion Gap Calculator Inputs and Outputs
An reliable anion gap calculator is only as accurate as the lab values entered into it. The main inputs are sodium, chloride, and bicarbonate, and the output is the calculated result. Some calculators also present the expected reference range so the user can immediately see whether the result is low, normal, or high.
Understanding the output requires more than comparing a number to a cutoff. A good calculator should help connect the result to the broader laboratory analysis. For example, a result slightly above the reference range may be meaningful in the context of symptoms or other abnormal chemistry findings, while a more marked elevation can suggest a more significant disorder in acid-base status.
Some calculators include albumin adjustment, which is useful because a low albumin can reduce the measured gap. This is one reason the raw result should be treated as a corrected value only after assessing the patient’s protein status and other findings. Using the calculator wisely helps improve clinical interpretation and reduce common mistakes.
Standard Anion Gap vs High Anion Gap
The usual range for the anion gap differs by lab, assay method, and whether potassium is part of the calculation. In general, a normal anion gap indicates that the balance between measured cations and anions is preserved, while a high anion gap implies extra unmeasured acids or anions are present.
A increased anion gap is especially relevant in the evaluation of metabolic acid buildup. In this setting, bicarbonate is often consumed as the body neutralizes excess acid, and the calculated gap increases as new unmeasured substances appear in the blood. This pattern points toward a form of acid-base imbalance that usually calls for further workup rather than simple observation.
A normal result does not always mean there is no problem. Some types of metabolic acidosis occur with a normal gap, particularly when bicarbonate is lost and chloride rises to replace it. That is why the anion gap should be used as one part of a broader serum chemistry review, not in isolation.
Common Causes of High Anion Gap
Several conditions can lead to a high anion gap, and the result often reflects build-up of acids or other nonmeasured substances. The most common are lactic acidosis, ketoacidosis, renal failure, and exposure to certain toxins.
Lactic acidosis occurs when lactate accumulates due to inadequate oxygen delivery, shock, severe infection, seizures, or other physiologic stressors. A elevated lactate level may align with a higher anion gap, although the two do not always track exactly. This makes the anion gap a valuable hint, but not a stand-in for direct testing.
Ketoacidosis develops when ketone bodies accumulate, often in diabetes, prolonged fasting, or heavy alcohol use. In this setting, the body generates an acid load that increases the gap. The result is commonly paired with low bicarbonate and a low pH on blood gas testing.
Renal failure can also result in a high gap because the kidneys are less capable to clear acids and preserve electrolyte balance. As renal function declines, retained acids gather and contribute to metabolic acidosis. This is one reason the anion gap is frequently assessed alongside kidney markers and overall chemistry findings.
Another critical category is toxin exposure. Toxic alcohols such as methanol or ethylene glycol can elevate the gap significantly. Salicylates can also trigger complex acid-base changes and should be considered when the history suggests ingestion or overdose. In these cases, the anion gap may be an initial alert of serious poisoning.
Typical Causes of a Decreased Anion Gap
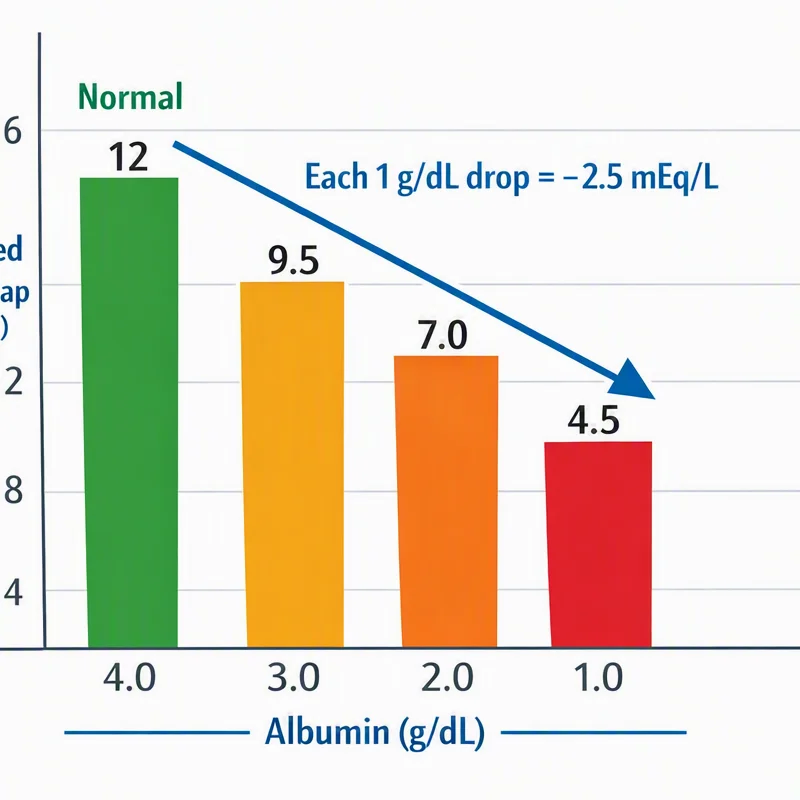
A reduced anion gap is rarer than a high one, but it can still be clinically important. One major cause is reduced albumin levels, since albumin is a negatively charged protein that accounts for much of the normal gap. When albumin falls, the measured gap may drop even if no new disorder is present.
Paraproteinemia is also an important cause. Specific atypical proteins, such as monoclonal immunoglobulins, can alter the charge balance in blood and reduce the apparent gap. This is why an unexpectedly low value may prompt a more careful review of the full chemistry profile and associated clinical picture.
Testing error should also be considered. Minor problems with specimen handling, measurement method, or reporting can create misleading results. If the number does not fit the patient’s condition or changes abruptly without explanation, repeating the test is often the initial practical step. In many cases, a low result is less about a dangerous disorder and more about a clue that the numbers need to be verified.
Why Albumin Affects an Anion Gap
Albumin is one of the main unmeasured anions in the blood, so shifts in its level can greatly affect the anion gap. When albumin is low, the gap may appear incorrectly reduced. This is why the corrected anion gap is often applied in people with low albumin, especially when assessing metabolic acidosis or other acid-base disorders.
The approach of albumin correction modifies the result upward to account for missing negative charge from low protein levels. This produces a more accurate corrected value and improves the usefulness of the test as a diagnostic aid. Without correction, a clinically important high gap can be missed if hypoalbuminemia is present.
Because albumin is a major circulating protein, any condition that reduces it can change the apparent balance of electrolytes. This means the raw number and the corrected number may tell different stories. A thoughtful interpretation should always consider the patient’s protein status, overall acid-base status, and the broader laboratory context.
Using the Anion Gap with Other Lab Findings
The anion gap becomes much more useful when interpreted with a blood gas, especially the pH and related measures such as base excess. Together, these results can confirm whether the body is acidemic, alkalemic, or compensating for a mixed disorder. This integrated approach improves clinical interpretation and gives a more complete picture of acid-base status.
As an example, a high anion gap with low pH and low bicarbonate strongly supports metabolic acidosis. If the blood gas shows an unexpectedly normal pH, there could be compensation or a mixed disorder masking the main process. The value of the anion gap is that it helps identify whether excess acids are present even before the pH fully reflects the problem.
Base excess adds another layer of information by estimating the amount of base needed to return blood to normal pH. When paired with the anion gap, it can help distinguish between acute and chronic processes and clarify whether the body is dealing with an acid load. Reviewing all of these numbers together is far more informative than relying on a single value.
When to Seek Medical Interpretation
An abnormal anion gap should be reviewed with a clinician when it is associated with symptoms, severe illness, or other abnormal lab findings. The result is most useful when interpreted in context, especially if there are signs of dehydration, confusion, shortness of breath, vomiting, abdominal pain, or altered mental status. These symptoms may signal a serious acid-base problem.
Clinician review is especially important when the value is markedly high or low, when there are critical values on the chemistry panel, or when the pattern suggests toxin exposure, severe renal function impairment, or an uncontrolled metabolic disorder. A calculator can support decision-making, but it cannot replace medical judgment or a full history and exam.
It is also wise to seek interpretation if the result doesn’t align with the overall picture, because lab error, sample issues, or missed albumin shifts can alter the outcome. The best approach is to use the anion gap as part of a more complete review of the patient’s condition, not as a single diagnosis.
Common Questions
What is an anion gap calculator used for?
An anion gap calculator is used to calculate the anion gap from common lab results, usually sodium, chloride, and bicarbonate. It helps with interpretation of electrolyte changes, especially when evaluating metabolic acidosis and other acid-base disorders. It is a helpful resource for reviewing serum electrolytes and identifying potential unmeasured acids.
How do you calculate anion gap from lab results?
The usual anion gap formula is sodium minus the sum of chloride and bicarbonate: sodium - (chloride + bicarbonate). Enter the values from the same sample into the anion gap calculator to get the result. Always compare the number to the lab’s reference range, since the expected interval can change by method and reporting system.
What does a high anion gap mean?
A high anion gap often means there are extra unmeasured anions in the blood, usually from an acid buildup. Common causes include lactic acidosis, ketoacidosis, renal failure, toxic alcohols, and salicylates. It is a key clue in the evaluation of metabolic acidosis, but it should be interpreted with blood gas findings and the clinical picture.
Can a low albumin level change the anion gap?
Yes. Hypoalbuminemia can lower the measured gap because albumin is an important negatively charged protein. In that situation, a corrected anion gap may be more reliable than the raw number. This albumin correction helps avoid missing a clinically important acid-base problem.
How should I respond if my anion gap is abnormal?
When your anion gap is abnormal, the next step is usually provider review of the full set of laboratory values, complaints, and related tests such as a blood gas. The meaning depends on whether the result is high, decreased, or affected by testing error, albumin changes, or another condition. Contact a medical professional right away if you have concerning signs or if the result is marked as a critical value.