What’s the Anion Gap?
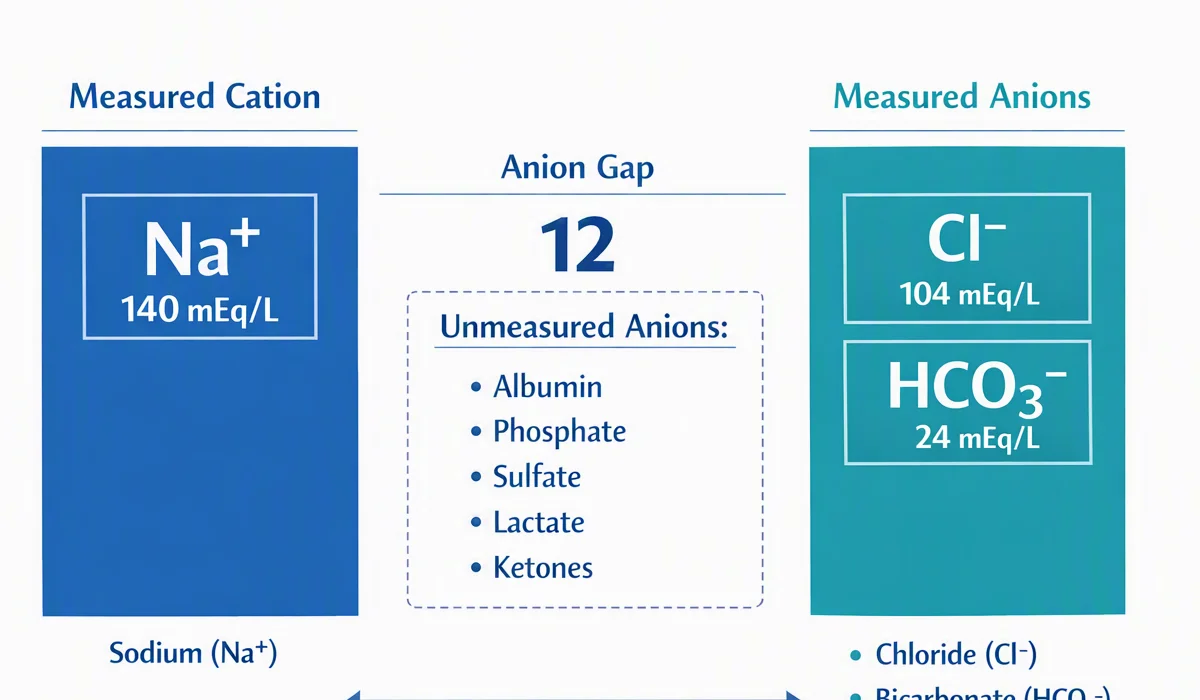
The anion gap is a calculated value that helps doctors interpret serum electrolytes and spot hidden problems in acid-base balance. It is not obtained directly. Instead, it is inferred from values typically reported on a basic metabolic panel or comprehensive metabolic panel, most often using sodium, chloride, and bicarbonate.
In plain language, the anion gap balances the positively charged ions and negatively charged ions in the blood. Because common lab panels do not capture every ion, the calculation acts as a practical gap-finder for unmeasured acids or other charged particles. That is why the anion gap calculator is often used as a rapid clinical tool during lab interpretation.
The result can provide a valuable diagnostic clue when a patient has a suspected acid-base disorder. It is especially useful when serum bicarbonate is low or when a blood chemistry panel suggests a metabolic abnormality. The anion gap value helps separate whether the cause of acidosis is likely to be buildup of acids or a loss of bicarbonate with compensatory chloride changes.
Although the exact anion gap range varies by laboratory and method, the concept remains the same: if the result is outside the expected reference range, it can suggest a hidden problem in the body’s buffer system.
When an Anion Gap Should Be Checked
It is appropriate to check the anion gap when there is concern for metabolic acidosis, especially if the cause is not obvious. It is a useful next step in evaluating unexplained acidosis, since it helps identify whether the problem is a high anion gap metabolic acidosis or a normal anion gap metabolic acidosis.
Ordering the anion gap is particularly helpful when a patient has abnormal bicarbonate on a basic metabolic panel or when the clinician suspects an acid-base disorder based on symptoms, history, or other lab results. In these instances, the calculation can quickly narrow the differential diagnosis and guide follow-up testing.
The anion gap may also be checked during a broader clinical assessment if the patient has signs of systemic illness, dehydration, altered mental status, or respiratory compensation. Because the result reflects changes in the concentration of major electrolytes, it can reveal a major metabolic derangement even before the full clinical picture is clear.
Typical reasons for ordering it include low serum bicarbonate, suspicion of toxic exposure, severe infection, poor perfusion, or worsening renal function. If the initial panel suggests a problem but does not explain why, the anion gap can be the missing link of the puzzle.
Common Patient Care Situations That Need an Anion Gap
Certain disorders commonly prompt an anion gap calculation because they are classic causes of metabolic acidosis. Such conditions often involve extra acid generation, reduced acid removal, or intake of agents that change blood chemistry.
Diabetic ketoacidosis is one of the most familiar examples. In this setting, ketone accumulation elevates the anion gap value and causes a clear high anion gap metabolic acidosis. The result can aid in confirm severity and track improvement alongside glucose and ketone testing.
Lactic acidosis is a further major indication. When tissues are not adequately perfused or the body is under significant physiologic stress, lactate can rise and increase the anion gap. This is often seen in sepsis, shock, hypoxia, or similar serious illnesses that require urgent evaluation.
Kidney failure is also a regular reason to check the anion gap. When the kidneys cannot eliminate acids effectively, unmeasured anions can accumulate in the blood. In severe renal impairment, the anion gap may rise and suggest worsening metabolic imbalance.
Toxin ingestion is a key use case. Poisoning with substances such as salicylates, ethylene glycol, or even certain patterns involving acetaminophen use can cause dangerous acid-base changes. In these cases, the anion gap can function as an early warning sign of toxic ingestion and should be interpreted rapidly in context.
As the clinical picture can evolve rapidly, the anion gap is often ordered alongside other blood chemistry tests to support timely decision-making.
How an Anion Gap Calculator Is Used
An anion gap calculator streamlines a calculation that is often part of everyday lab interpretation. Clinicians enter the relevant electrolyte values, usually from a basic metabolic panel or comprehensive metabolic panel, and the tool returns the result immediately.
Most commonly, the calculator uses sodium, chloride, and bicarbonate. Since the result depends on those exact numbers, the calculator is only as reliable as the labs used. A small change in any one of those values can alter the outcome, especially when the numbers are already near the edge of the expected range.
One important feature is albumin correction. Because albumin is a major unmeasured anion, hypoalbuminemia can make the anion gap appear falsely normal or low. A corrected result can therefore be more useful than the raw value. The corrected anion gap is particularly useful when evaluating acidosis in hospitalized patients or anyone with low protein levels.
The calculator also supports interpretation of serum bicarbonate changes by connecting the electrolyte pattern to a likely acid-base process. This makes it easier to decide whether a patient’s findings reflect metabolic acidosis, another acid-base disorder, or a mixed problem that needs more testing.
In practice, the tool is not a diagnosis by itself. It is a organized way to support clinical assessment, support a suspicion, and prompt the next step in workup.
High Anion Gap vs Typical Anion Gap
A elevated anion gap often suggests that undetected acids are accumulating in the blood. This pattern is often seen in high anion gap metabolic acidosis, where the body is producing acids faster than it can eliminate them. Frequent causes include ketoacidosis, lactic acidosis, kidney failure, and toxin ingestion.
A standard anion gap does not rule out acidosis. Instead, it may point toward normal anion gap metabolic acidosis, also called hyperchloremic acidosis. In this pattern, bicarbonate is depleted and chloride rises to maintain electrical balance. This can occur with gastrointestinal bicarbonate loss, certain kidney tubular disorders, or other processes that lower serum bicarbonate without increasing unmeasured anions.
It is also important to remember that not every acid-base change means acidosis. A patient may have a mixed disorder in which the anion gap is altered alongside metabolic alkalosis. For example, vomiting, diuretic use, or volume depletion can affect the overall picture and complicate lab interpretation.
Understanding the difference between a elevated anion gap and a typical anion gap helps clinicians decide which disease processes are more likely and which tests should come next. In other words, the value is not just a number; it is a map for reading the body’s current acid-base state.
What May Influence the Result?
Several factors can affect the reported anion gap and should be reviewed before reaching conclusions. One of the key is hypoalbuminemia. Because albumin carries negative net charge, low albumin can reduce the measured anion gap and conceal an hidden acid problem. That is why albumin correction matters so much in real-world lab interpretation.
Lab error is also a possible concern. Specimen handling problems, analyzer variation, or transcription mistakes can all cause misleading numbers. If the result does not fit the clinical picture, repeating the chemistry panel may be appropriate.
Changes in pH can also affect interpretation. The anion gap itself is not a direct pH measurement, but it is part of the overall acid-base status. If the patient has significant acidemia or alkalemia, the rest of the workup may need to include gas analysis and repeat chemistry to clarify the full pattern.
Potassium is in some cases included in an alternate form of the calculation, though many routine versions do not use it. Even when it is not part of the formula, shifts in potassium can still matter because they often accompany a more general electrolyte imbalance. In short, the anion gap should always be interpreted alongside the rest of the blood chemistry and the patient’s symptoms.
When You Should Seek Further Testing or Clinical Evaluation
An unusual result often prompts more testing rather than a final conclusion. If the anion gap is elevated, or if unexplained acidosis remains, clinicians may order an arterial blood gas to better define the acid-base status and respiratory compensation. This is especially useful when the severity of illness is unclear or when there may be a mixed disorder.
Repeat testing is also appropriate when the result is unexpected, inconsistent with the clinical picture, or Get more information potentially affected by sampling issues. A repeat chemistry panel can confirm whether the abnormality is still present or transient.
Increasing clinical symptoms should always guide urgency. Symptoms such as confusion, vomiting, rapid breathing, marked weakness, dehydration, or declining mental status may indicate a more significant underlying process. In that setting, the anion gap is just one piece of a broader evaluation.
Because an abnormal value can reflect a substantial electrolyte imbalance or major metabolic abnormality, the result should not be ignored if it matches the patient’s condition. Instead, it should trigger timely evaluation of renal function, toxic exposure, lactate, ketones, and other relevant studies.
FAQ
What range is considered normal for the anion gap?
The anion gap normal range depends on the laboratory method and whether the calculation includes potassium. Many labs report a relatively narrow range, but the exact reference range can vary. Always interpret the result using the lab’s own reference range rather than relying on a fixed universal value.
When should the anion gap be checked with lab tests?
It should be ordered when there is concern for metabolic acidosis, an acid-base disorder, or unexplained acidosis. It is especially useful if the basic metabolic panel or comprehensive metabolic panel shows low bicarbonate or if symptoms suggest a underlying metabolic issue.
Why does the anion gap important in metabolic acidosis?
It is used to determine the cause of metabolic acidosis. A high anion gap suggests accumulation of unmeasured acids, while a normal anion gap points toward bicarbonate loss with chloride replacement. That distinction guides the next steps in assessment and treatment.
Does low albumin change the anion gap result?
It can. Hypoalbuminemia can lower the measured anion gap and hide an abnormality. That is why albumin adjustment or albumin correction is important when reading results, especially in admitted or critically ill patients.
How should it be handled if the anion gap is high?
A high result should lead to assessment of the full clinical picture and assessment of causes such as diabetic ketoacidosis, lactic acidosis, kidney failure, or toxin ingestion including salicylates and ethylene glycol. Depending on the situation, clinicians may order an arterial blood gas, repeat testing, and additional labs to assess the cause of the acid-base disturbance.